
CYP2C19 and Your SSRIs: When Citalopram, Escitalopram or Sertraline Needs a Different Dose

CYP2C19 and Your SSRIs: When Citalopram, Escitalopram or Sertraline Needs a Different Dose
A report comes back: CYP2C19 poor metabolizer. Your patient is on escitalopram and doing fine. Do you change anything? Now picture the same patient on citalopram instead. CPIC’s advice for a poor metabolizer is much the same for both — but the dose ceilings are not: citalopram carries an FDA 20 mg/day limit in poor metabolizers that escitalopram’s label never sets, and the DPWG caps differ too. Same gene, same enzyme — yet the ceiling, and sometimes which body acts, change with the drug. A CYP2C19 result is only useful once you can say, for the exact drug in front of you, whether it calls for a lower dose or slower titration, an alternative, or no genotype-driven change — and who says so.
The 30-second version
- Act on a CYP2C19 phenotype only when a named body ties it to an action for the specific drug. The answer is usually one of three — adjust the dose or titration, consider an alternative, or make no genotype-driven change — and the source (CPIC, DPWG, or the FDA label) is named separately. One body's recommendation is never another's.
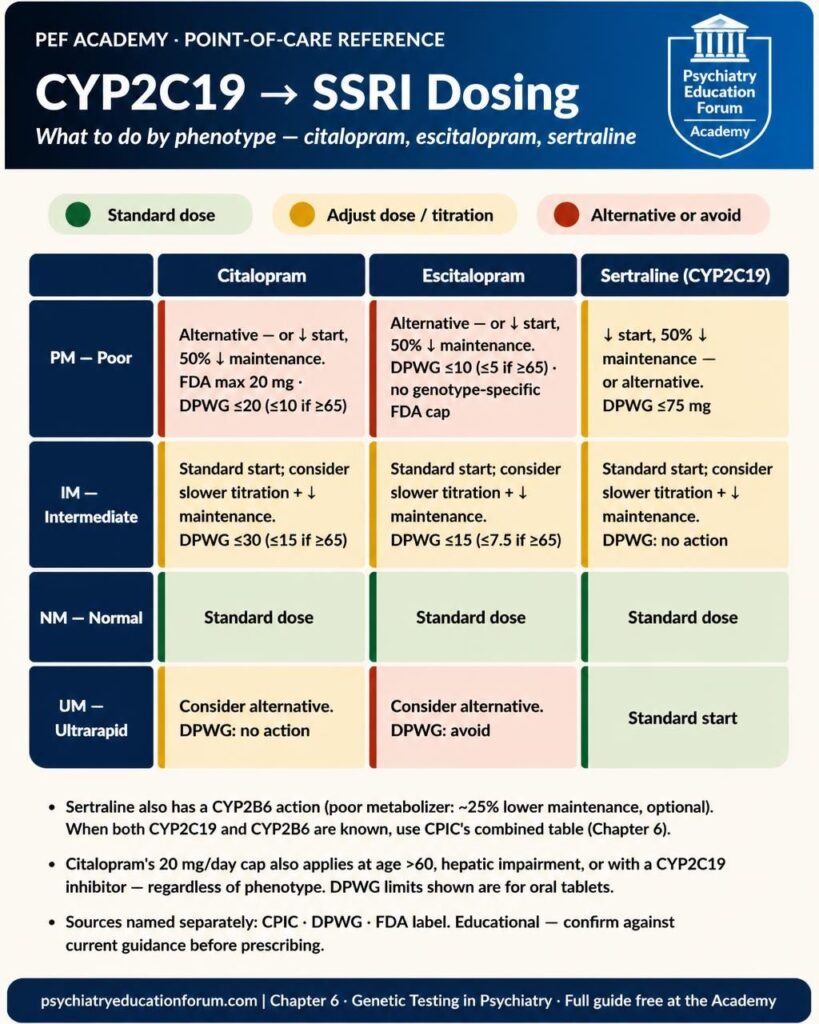
- Citalopram and escitalopram share one CPIC table. Poor metabolizers — consider an alternative, or if used, a lower start, slower titration and a 50% lower maintenance dose (strong). Intermediate — standard start, then consider slower titration and a lower maintenance dose (moderate). Ultrarapid — consider an alternative (strong), or — if the drug is kept and response is inadequate — a higher maintenance dose within label limits.
- The citalopram 20 mg/day cap does not transfer to escitalopram. The FDA citalopram label caps CYP2C19 poor metabolizers at 20 mg/day for QT reasons; escitalopram’s label sets no genotype-specific cap (the usual FDA maximum is 20 mg/day; 10 mg once daily is the recommended dose for most older adults and in hepatic impairment).
- CPIC and DPWG disagree at the top end. For citalopram ultrarapid metabolizers, CPIC says consider an alternative while DPWG says no action; for escitalopram ultrarapid, both act (CPIC alternative, DPWG avoid).
- Sertraline is a different question. CPIC addresses it on CYP2C19 and CYP2B6; DPWG only caps CYP2C19 poor metabolizers at 75 mg/day and makes no CYP2B6 recommendation. When both results are in hand, CPIC's combined-phenotype table gives the recommendation — not the two single-gene rows read independently.
- Some results call for no genotype-driven change. Sertraline CYP2C19 ultrarapid or normal metabolizers: CPIC advises the standard starting dose, DPWG no action (a concurrent CYP2B6 result can change this — use CPIC’s combined-phenotype table). Read the call for context and don't change a stable, effective, tolerated regimen on a phenotype alone — while still reassessing dose, QT risk factors, interacting drugs and any label limit.
Why does CYP2C19 matter for these three drugs?
Because it strongly shapes drug exposure — alongside other metabolic pathways, interacting drugs and patient factors. Citalopram and escitalopram are extensively metabolized by CYP2C19 to much less potent metabolites, so a poor metabolizer tends to run higher levels and an ultrarapid metabolizer lower ones.
For citalopram and escitalopram, that higher exposure in poor metabolizers raises the risk of side effects — and, for citalopram, a QT concern specific enough that the FDA label sets a hard genotype-based dose limit. (Escitalopram’s label documents an exposure–QT relationship too, but sets no genotype-specific cap.) Lower exposure in ultrarapid metabolizers can lower the chance of benefit, though it doesn’t determine an individual’s response. Sertraline is handled by several enzymes — CYP2C19, CYP2B6, CYP2D6 and others — with CYP2C19 the major pathway and no evidence supporting a CYP2D6-guided dose adjustment, which is exactly why the sertraline recommendations hang on CYP2C19 and CYP2B6, not CYP2D6.
One caution before any number: the reported phenotype is a genotype-based prediction. Interacting medicines and other clinical factors can shift functional enzyme activity (phenoconversion), so a CYP2C19 call is read together with the current medication list, not in isolation.
| Drug | Gene(s) with an action | Who sets it |
|---|---|---|
| Citalopram | CYP2C19 | CPIC, DPWG, and the FDA label (20 mg/day cap in PMs) |
| Escitalopram | CYP2C19 | CPIC and DPWG (no genotype-specific FDA cap) |
| Sertraline | CYP2C19 + CYP2B6 | CPIC (both genes); DPWG (CYP2C19 only) |
Citalopram and escitalopram: what each body says
CPIC gives one shared table for both. The practical split is: poor metabolizers get a lower dose or a switch; intermediate metabolizers get a cautious standard start; ultrarapid metabolizers get a switch considered. Then the drug-specific label and DPWG caps layer on.
| Phenotype | Citalopram | Escitalopram |
|---|---|---|
| Poor / likely poor | CPIC: consider an alternative; if used, lower start, slower titration, 50% lower maintenance (strong). DPWG: ≤20 mg/day (≤10 if ≥65 y). FDA label: max 20 mg/day (QT; same cap for age >60, hepatic impairment, or a CYP2C19 inhibitor). | CPIC: same — alternative, or lower start + slower titration + 50% lower maintenance (strong). DPWG: ≤10 mg/day (≤5 if ≥65 y). No CYP2C19-specific FDA cap (usual max 20 mg/day). |
| Intermediate | CPIC: standard start, then consider slower titration and lower maintenance (moderate). DPWG: ≤30 mg/day (≤15 if ≥65 y). | CPIC: same (moderate). DPWG: ≤15 mg/day (≤7.5 if ≥65 y). |
| Normal | CPIC: standard (strong). | CPIC: standard (strong). |
| Ultrarapid | CPIC: consider an alternative (strong). DPWG: no action. | CPIC: consider an alternative (strong). DPWG: avoid escitalopram. |
Note: for citalopram, the FDA 20 mg/day maximum also applies — regardless of CYP2C19 phenotype — to patients over 60, those with hepatic impairment, and those taking a CYP2C19 inhibitor. A DPWG ceiling never licenses exceeding a lower applicable FDA limit. The DPWG limits shown are for oral tablets, applying the lower dose from age 65; other formulations (e.g., oral drops) may carry different DPWG limits.
Two things to hold onto. First, the citalopram 20 mg/day ceiling in poor metabolizers is a QT-safety limit set by the FDA label — and DPWG independently caps citalopram poor metabolizers too — but it is a citalopram action. It does not transfer to escitalopram, whose label sets no genotype-specific cap. Second, for rapid metabolizers CPIC does not switch pre-emptively: it considers a higher maintenance dose or a switch only after an inadequate response, and any citalopram increase stays within the label ceiling.
Why is sertraline a different question?
Because it is the one of the three where a second gene, CYP2B6, carries its own recommendation — and where the two genes have to be read together, not separately.
CPIC addresses sertraline on two genes — and only CPIC gives the CYP2B6 recommendation. Here is each gene, by phenotype:
| Gene & phenotype | CPIC action | DPWG |
|---|---|---|
| CYP2C19 — PM | Lower start, slower titration, 50% lower maintenance, or an alternative (moderate) | ≤75 mg/day |
| CYP2C19 — IM | Standard start; consider slower titration and lower maintenance (moderate) | No action |
| CYP2C19 — NM / RM / UM | Standard starting dose | No action |
| CYP2B6 — PM | Lower start, slower titration, 25% lower maintenance, or an alternative (optional) | No CYP2B6 action |
| CYP2B6 — IM | Standard start; consider slower titration and lower maintenance (optional) | No CYP2B6 action |
| CYP2B6 — NM / RM / UM | Standard starting dose | No CYP2B6 action |
The sertraline FDA label carries no CYP2C19 or CYP2B6 dose action.
Where CPIC, DPWG and the label disagree
In three places that matter at the point of care — and merging them is the most common error.
| Where they diverge | What to watch |
|---|---|
| Citalopram, ultrarapid | CPIC: consider an alternative. DPWG: no action. Same drug, same phenotype, different advice — name which one you are following. |
| The citalopram cap | The FDA 20 mg/day poor-metabolizer limit (QT) is a citalopram action. It does not transfer to escitalopram, whose label sets no genotype-specific cap. |
| “Rapid” metabolizer | DPWG counts *1/*17 as normal and only *17/*17 as ultrarapid — so a report’s “rapid” call has no DPWG action behind it. |
When does a result not call for a change?
When no named body ties a genotype action to the combination, or when a stable, effective, well-tolerated regimen does not automatically require a genotype-driven change. “No genotype-driven change” is not “no reassessment”: dose, QT risk, interacting drugs and any label limit still apply. An explicit "standard starting dose" is itself an answer — read for context, don't invent an action.
The clearest example is sertraline in ultrarapid or normal metabolizers: CPIC advises the standard starting dose, DPWG no action, and the label nothing. The metabolizer call is read for context — and if a CYP2B6 result is also reported, read with the combined table — not acted on. And a stable, effective, well-tolerated regimen does not automatically require a genotype-driven change, though dose, QT risk, interacting drugs and any label limit are still reviewed — a citalopram poor metabolizer above 20 mg/day is over the FDA cap even if the regimen feels settled. Knowing when a result should change nothing is half of what it is good for. To close the loop on the patient at the top: a stable, well-tolerated escitalopram regimen with a new CYP2C19 poor-metabolizer result warrants a regimen review — exposure is higher, and escitalopram still carries a CPIC recommendation — but a working, well-tolerated treatment is not switched on the genotype alone.
Chapter 6 turns this into a point-of-care decision.
Chapter 6 of Genetic Testing in Psychiatry gives you the full by-phenotype table for all three SSRIs with each source named separately, the combined CYP2C19/CYP2B6 table for sertraline, a two-minute bedside panel, a lower/switch/ignore triage, a patient script and a copy-paste EMR note. The course closes with a one-screen drug–gene action grid for every pair it acts on.
Join to read Chapter 6 → See the full course →Table of contents
Chapters 1 and 8 are free to read. The rest are included with Academy membership.
- 1Should I Order a Pharmacogenomic Panel? Free · read now
- 2Gene Tests to Order Before Carbamazepine, Oxcarbazepine, Valproate or Clozapine Members
- 3A Patient Hands You a Report: What to Act On, What to Ignore Members
- 4Why Doesn't the Patient's Genotype Match Their Drug Response? Members
- 5CYP2D6: When to Lower, Switch or Ignore Members
- 6CYP2C19 and CYP2B6: Citalopram, Escitalopram, Sertraline Members · this brief
- 7Does Smoking or Another Medication Matter More Than Genotype? Members
- 8Should an MTHFR Result Change Treatment? Free · read now
- 9Should I Act on SLC6A4, HTR2A or ANK3? Members
- ★Drug–Gene Action Grid: one-screen lookup for the whole course Members
Every chapter, every series, one membership.
Academy membership opens every chapter in this course and the rest of the Academy library, written for prescribers at the point of care.
See membership plans →


Responses