
Long-acting injectable vs oral antipsychotics in bipolar disorder: should LAIs come earlier?

Long-acting injectable vs oral antipsychotics in bipolar disorder: should LAIs come earlier?
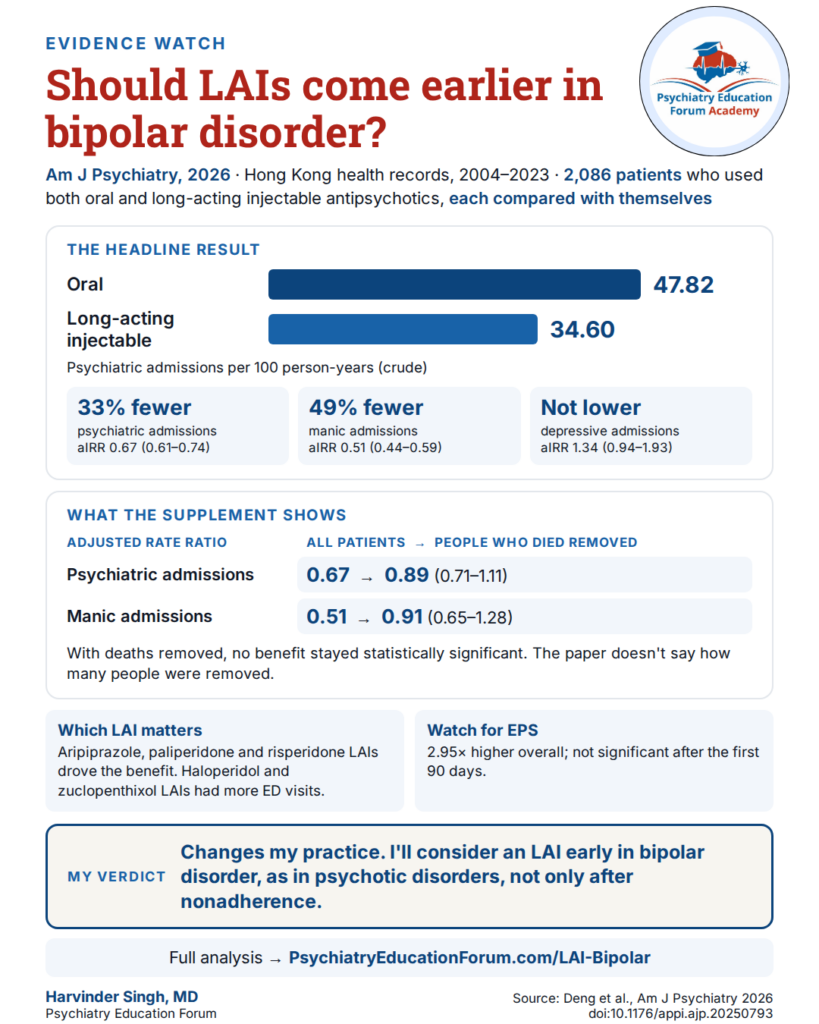
A 20-year Hong Kong study of 2,086 patients, read for the prescriber: the answer first, then the questions you'd ask.

Deng EK, Huang C, Yan VKC, et al. Comparison of Long-Acting Injectable and Oral Antipsychotics in Bipolar Disorder. Am J Psychiatry. Published online September 9, 2026. PMID 42711749 · doi:10.1176/appi.ajp.20250793
The 60-second read
Peer-reviewed · Observational- Applies toPeople with bipolar disorder on an oral antipsychotic who have needed hospital or ED care, when you're weighing an LAI
- Biggest caveatWhen people who died during follow-up were removed, no benefit stayed statistically significant (supplement, Table S5)
- Second caveatMost injectables were first-generation; the two CANMAT ranks for maintenance were the least used
- Our poll44% already offer LAIs early · 33% reserve them · 22% would start earlier · 0% wait for more data
1Who this is about, and who it isn't
About
| Patients | 2,086 people with bipolar disorder who used both oral and LAI antipsychotics (of 17,841 in the database); mean age 37.8 |
|---|---|
| Comparison | Time on an LAI alone vs time on an oral alone, within the same person |
| Outcomes | ED visits and hospital admissions by cause; extrapyramidal symptoms |
| Follow-up | Mean 11.6 years |
| Data | Hong Kong public hospitals (CDARS), 2004–2023 |
| Required | At least one outcome event during follow-up |
Not about
| Oral only | Patients who never received an LAI |
|---|---|
| No hospital contact | Anyone with no ED visit or admission during follow-up |
| Milder relapses | Episodes managed without a hospital visit (not captured) |
| Bipolar subtype | Bipolar I vs II was not recorded |
If that's your patient, you can stop here.
2The numbers, made usable
Read these with care: the crude figures count admissions, not patients, and come before adjustment. One person can contribute several admissions. They describe what happened during LAI periods. They are not admissions prevented, so I haven't converted them into a number needed to treat.
- Manic-episode admissions: adjusted aIRR 0.51 (0.44–0.59).
- Mixed-episode admissions: aIRR 0.31 (0.14–0.66), based on only 11 events in LAI periods.
- Depressive-episode admissions went the other way in crude rates (20.41 on LAI vs 14.74 on oral). The adjusted aIRR was 1.34 (0.94–1.93), not significant.
- Extrapyramidal symptoms: aIRR 2.95 (1.40–6.22) overall, no longer significant once the first 90 days were excluded. This is a pooled figure. When each LAI was compared with its own oral form, none differed significantly on EPS.
- ED visits: the crude rate was higher on LAI (154.08 vs 144.98 per 100 person-years). The 15% reduction (aIRR 0.85) comes from the within-person, adjusted comparison.
- Subgroups: over age 65, there was no statistically significant reduction in ED visits or admissions. That is not the same as proof of no benefit. Women had more depressive-episode admissions on LAI. The association was stronger in people who started an LAI within 2 years of diagnosis (47% fewer ED visits and 48% fewer admissions) than in later starters (13% and 22%). The paper doesn't report a test of whether that difference is real, and comparing two groups of patients can't show that starting earlier improves outcomes.
3The detail the abstract leaves out
The authors ran 10 sensitivity analyses and summarise them as "aligned with the main findings." One of them removed everyone who died during follow-up. They added it because deaths from "severe disease relapses (e.g., suicide) or treatment side effects" can bias this design. In that analysis, no benefit stayed statistically significant, and the point estimates moved close to 1.
The paper doesn't say how many people were removed, so the reason is uncertain. It could be a smaller sample, a different set of patients remaining, or something else. The point estimates moved toward 1, rather than the intervals simply widening. This doesn't prove the main results are wrong. It does raise a real question about how robust they are, and "aligned with the main findings" doesn't describe it.
Two more results from the same table:
- Patients with steady prescriptions (at least 10 antipsychotic prescriptions a year for more than 5 years, which the authors use as a marker of better adherence): the ED benefit disappeared (aIRR 1.06, 1.00–1.12). Psychiatric (0.77, 0.69–0.86) and manic (0.60, 0.50–0.71) admissions stayed lower.
- The depressive signal became significantly worse on LAI in three analyses: excluding people later diagnosed with schizophrenia, aIRR 1.58 (1.08–2.31); adjusting for calendar year, 1.45 (1.01–2.09); counting principal diagnoses only, 1.61 (1.15–2.25).
The methods also describe an analysis that excludes the 30 days before each treatment switch, the main test of whether relapses drove the switch to an LAI. Its overall results do not appear in Table S5.
4How this fits the existing evidence
CANMAT/ISBD 2018 addresses LAIs in its section on treatment-refractory bipolar disorder:
"In patients who are non-adherent, psychosocial strategies such as psychoeducation should be used to improve treatment adherence. If ineffective, long-acting injectable medications should be offered."
For maintenance in bipolar I, CANMAT ranks two injectables: aripiprazole once-monthly (first-line) and risperidone LAI (second-line, "no clear efficacy in depressive episode prevention"). Those two were the least used in this study. A 2023 summary of the guidelines by CANMAT authors, which adds newer evidence but is not a formal revision, keeps both rankings unchanged.
The authors also compared each injectable with its own oral form. These are smaller, exploratory comparisons; the paper doesn't report a correction for multiple testing. Read them as hypothesis-generating. Only statistically significant differences are listed, with 95% CIs:
| LAI | Generation | vs its own oral form |
|---|---|---|
| Aripiprazole | Second | Fewer ED visits 0.61 (0.50–0.75), admissions 0.63 (0.48–0.81), psychiatric 0.37 (0.25–0.56), manic 0.43 (0.23–0.80) and depressive admissions 0.20 (0.04–0.95). The only LAI with fewer depressive admissions; note the wide interval. |
| Paliperidone | Second | Fewer admissions 0.59 (0.44–0.80), psychiatric 0.42 (0.28–0.62) and manic admissions 0.32 (0.23–0.43) |
| Risperidone | Second | Fewer admissions 0.37 (0.17–0.79) and psychiatric admissions 0.31 (0.13–0.75) |
| Flupenthixol | First | Fewer ED visits 0.64 (0.52–0.79) and manic admissions 0.64 (0.42–0.98); more admissions 1.49 (1.05–2.13) and non-psychiatric admissions 1.83 (1.06–3.16) |
| Haloperidol | First | More ED visits 1.49 (1.33–1.67) |
| Zuclopenthixol | First | More ED visits 3.08 (1.48–6.41); fewer manic admissions 0.61 (0.47–0.80) |
| Source | Type | What it says about LAIs in bipolar disorder |
|---|---|---|
| Deng et al. 2026 | Observational, self-controlled | Fewer psychiatric, manic and mixed admissions than oral; no reduction in depressive admissions; mostly first-generation LAIs |
| CANMAT/ISBD 2018 | Guideline | In refractory illness with nonadherence, offer an LAI if psychoeducation fails; aripiprazole once-monthly first-line, risperidone LAI second-line for maintenance |
5What the authors concluded vs. what the data support
The abstract concludes: "These findings support the use of LAIAs for bipolar disorder, with close monitoring for extrapyramidal symptoms during initiation." The discussion goes further. Guidelines that reserve LAIs for severe cases or established nonadherence should be reconsidered: "our findings support reassessment of this conservative approach."
The strongest part of the data is manic and mixed relapse. Those results held across most checks, and an unmeasured confounder would need a rate ratio of 2.78 (manic) or 2.04 (psychiatric admissions) with both treatment and outcome to explain them away. Three things weaken a broad "LAIs earlier" message:
- When each drug was compared with its own oral form, the benefit came from specific drugs. Two of the first-generation injectables had more ED visits.
- The analysis without people who died lost every significant benefit, and the abstract doesn't mention it.
- "Early vs late" initiation compares two groups of patients. It doesn't test what happens when you start earlier.
6What it doesn't answer
- Is it the injection or the adherence? The data contain no adherence measure. In the steady-prescription group, admissions stayed lower but the ED benefit was gone.
- Would modern second-generation LAIs alone show the same class effect? Aripiprazole and risperidone LAIs made up 230 and 109 of the patients prescribed LAIs.
- Bipolar I vs bipolar II. Subtype was not recorded, and neither were illness severity or dose.
- Depression. Do LAIs raise depressive admissions, especially in women? The point estimate leans that way and reaches significance in some analyses.
- The deaths analysis. How many people were removed, and why does the benefit fade without them?
- Other health systems. Only Hong Kong public hospitals are included, and they cover most admissions there.
Does this change practice?
This study has changed my attitude: I'll now consider an LAI early in bipolar disorder, as we do in psychotic disorders, rather than waiting for nonadherence.
In my practice, I have seen LAIs used far more often for psychotic disorders than for mood disorders. My inclination has been to consider an LAI in bipolar disorder mainly when nonadherence was the problem. This study has changed my attitude toward considering them early, as we already do in psychotic disorders.
Become an Academy member
Full access to every course and Rapid Decision Guide, including the Bipolar Disorder course.
Sources
- Deng EK, Huang C, Yan VKC, et al. Comparison of long-acting injectable and oral antipsychotics in bipolar disorder. American Journal of Psychiatry. Published online September 9, 2026. doi.org/10.1176/appi.ajp.20250793. PMID 42711749. Observational self-controlled case series; the online supplement (Tables S5–S7) holds the sensitivity analyses and drug counts. Funded by the National Natural Science Foundation of China. Disclosures include research donations from Johnson & Johnson (one author) and consulting for Janssen and Alkermes (another author).
- Keramatian K, Chithra NK, Yatham LN. The CANMAT and ISBD guidelines for the treatment of bipolar disorder: summary and a 2023 update of evidence. Focus. 2023;21(4):344–353. doi.org/10.1176/appi.focus.20230009. Narrative summary by guideline authors; not a formal guideline revision.
- Yatham LN, Kennedy SH, Parikh SV, et al. CANMAT and ISBD 2018 guidelines for the management of patients with bipolar disorder. Bipolar Disorders. 2018;20:97–170. doi.org/10.1111/bdi.12609. Guideline.


Responses