
Lithium and a Falling eGFR: Is There a Number at Which You Must Stop, and Why Not Wait for 30 to Decide?

Lithium and a Falling eGFR: Is There a Number at Which You Must Stop, and Why Not Wait for 30 to Decide?
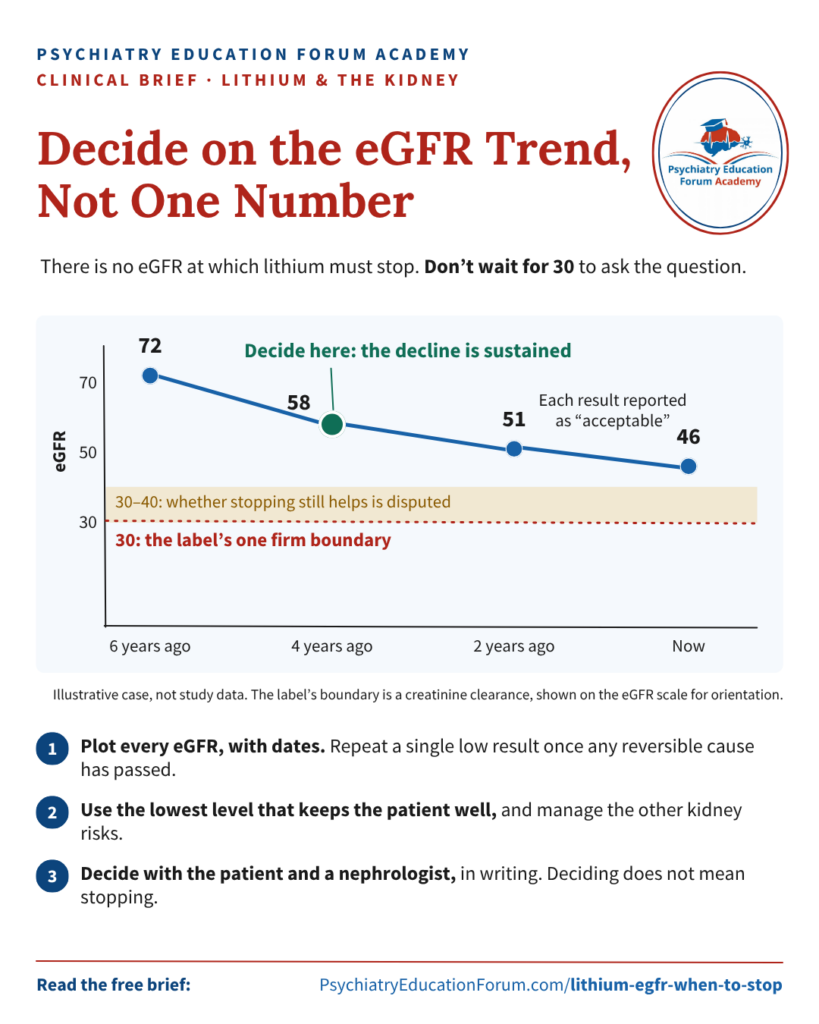
The letter from primary care is short. The eGFR is 46, the patient now has “CKD stage 3,” and should lithium be stopped? Two reflex answers follow. One is to stop lithium now, because the kidney number has crossed a line. The other is to carry on until the eGFR reaches 30, because that is the number in the label. Both treat the decision as a threshold. It is not one. No number above the label’s boundary forces a stop, and waiting for that boundary means making the most important decision in long-term lithium care at the moment the evidence is least settled.
The 30-second version
- There is no eGFR at which lithium must stop. The label’s one firm boundary is that it does not recommend lithium in severe kidney impairment, a creatinine clearance below 30 mL/min. Above that, the decision is a judgement. CANMAT says a strict cut-off is difficult to set.
- The trend is the signal, not the number. The label says progressive or sudden changes in kidney function, even within the normal range, call for re-evaluation.
- Moderate decline is common; severe disease is not. Severe kidney disease on lithium is uncommon and concentrated in older patients with long exposure.
- Stopping can slow the decline. In a 2025 Swedish study, the yearly fall almost levelled off after lithium stopped, and returned when it was restarted. How much stopping helps once kidney function is badly reduced is still disputed.
- Decide when a sustained decline is first seen. Deciding does not mean stopping. For many patients the answer is a lower level, closer monitoring and active management of the other kidney risks.
- The decision is psychiatric as well as renal. Kidney benefit has to be weighed against the risk of relapse and suicide on stopping.
Is there an eGFR at which lithium must stop?
No. The label draws one boundary, at a creatinine clearance below 30 mL/min. Every other number you will hear quoted is a guide for when to act, not a rule that decides for you.
The US lithium label does not recommend lithium in severe kidney impairment, which it defines as a creatinine clearance below 30 mL/min. It asks for kidney function to be checked before and during treatment, and for lower doses, slow titration and frequent levels when kidney function is reduced. It does not give an eGFR at which lithium has to stop. Here is what the commonly quoted numbers actually mean.
| Number you hear | Where it comes from | What it does, and does not, mean |
|---|---|---|
| Creatinine clearance below 30 | The US lithium label | Lithium is not recommended. The one firm boundary. |
| eGFR 30–40 | A 2026 international expert review | Below this range, improvement after stopping is less likely, in the review’s view. Not a stop rule, and disputed (see below). |
| eGFR below 60 | The CKD stage 3 boundary | Common in older adults. CANMAT says this is exactly why a strict cut-off for stopping lithium is difficult to set. |
| “Within the normal range” | The laboratory report | Not reassurance if it is falling. The label asks for re-evaluation of progressive change even in the normal range. |
If not a number, what should make me act?
A sustained fall across several results. Read eGFR as a series, and repeat a single low result once any reversible cause has passed.
Lithium’s effect on the kidney is slow, and slow harms are the ones clinical systems handle worst. Each result is seen by a different person, each is a little lower than the last, and each is still “acceptable.” A psychiatry editorial on eGFR in lithium monitoring suggested investigating a progressive fall across three or more serial tests. The 2026 expert review makes the same point: decisions should follow the trajectory, not a single value.
Two traps sit on either side of the trend.
- One low result can be temporary.A fall after a toxicity episode, dehydration or a new interacting drug may partly recover. In a Swedish series of lithium-treated patients with at least one eGFR below 30, about half had a transient fall followed by improvement. Repeat the result once the cause has passed.
- A slow fall can hide in the normal range.eGFR falls with age in everyone. The question is whether this patient’s rate is steeper than age alone explains, and that is exactly what a nephrologist can help judge.
For when to involve nephrology, the UK NICE kidney guideline gives criteria that apply to any adult with chronic kidney disease, and lists lithium among the medicines that need eGFR monitoring at least once a year.
| NICE NG203: refer to nephrology if | In plain terms |
|---|---|
| A sustained fall in eGFR of 25% or more with a change in eGFR category within 12 months | A big drop in a year |
| A sustained fall of 15 mL/min or more per year | A fast, steady slope |
| A five-year risk of kidney replacement therapy above 5% (Kidney Failure Risk Equation) | High predicted risk of needing dialysis |
| Significant albuminuria | Protein in the urine, which is not the typical lithium picture |
Who is most at risk?
Patients with long exposure, older age, higher levels, previous toxicity episodes and other kidney risks. Most of these you can see coming.
Moderate decline is common. A 2026 Dutch prospective cohort of 196 long-term users found that most lost kidney function faster than the general population, and that higher lithium levels and longer treatment went with faster decline. Severe disease is the tail of the distribution, not the body: a Swedish laboratory study with follow-up of more than 35 years found severe chronic kidney disease uncommon overall, with most cases after 70.
| Risk factor | What you can do |
|---|---|
| Long duration of treatment | Nothing directly, which is why the other factors matter more as the years pass |
| Older age | Monitor more often, and review the target level as the patient ages |
| Higher serum levels | Use the lowest level that keeps the patient well |
| Previous toxicity episodes | Prevent the next one: sick-day rules and interaction checks |
| Diabetes, high blood pressure, heart disease, diuretics, regular NSAIDs | Manage them actively; plan a level whenever a drug that affects lithium clearance starts |
| Higher creatinine before lithium started | Closer monitoring from the start |
Does stopping lithium actually help the kidney?
The best direct evidence says it can slow the decline. How much it helps once kidney function is badly reduced is still disputed.
| Study | What it found | Limits |
|---|---|---|
| Swedish mirror-image study, 2025 (168 patients, at least 4.5 years on lithium) | The yearly fall in eGFR almost levelled off after stopping, for five years. Larger benefit at lower eGFR: the slope improved in 9 of 10 patients below 30. The decline returned in those who restarted. | Retrospective, one region, possible selection bias |
| Dutch prospective cohort, 2026 (196 patients; 33 followed after stopping) | Decline numerically lower after stopping, but not statistically significant | Small numbers, mostly well-preserved kidney function; the authors cite limited power and short follow-up |
| 2023 review and 2026 expert review | Patients who stop with preserved function tend to stabilise or improve; with more damage, decline often continues. Below eGFR 30–40, improvement is less likely. | Expert interpretation of mixed, mostly small studies |
| Swedish study of severe kidney impairment, 2025 | Among patients reaching stage 4 disease, survival did not differ between those who stopped and those who continued. The authors suggest keeping lithium in most cases at that stage. | Possible selection bias; sits against the label’s boundary |
Read closely, the Dutch and Swedish findings are less opposed than they first appear: the Dutch study had few patients who stopped, and its numbers moved in the same direction. The real disagreement is about patients whose kidney function is already badly reduced. That is exactly why the decision should not be left until then.
So when, and how, should I decide?
This month, once a sustained fall is confirmed, with the patient and a nephrologist, and in writing.
- Plot every eGFR you can find, with dates.Decide on the trend, not on the latest number.
- Rule out a reversible cause.A toxicity episode, dehydration, an NSAID, or a new ACE inhibitor, ARB or diuretic.
- Check the rest of the picture.A urine protein test, blood pressure, glucose, calcium and a 12-hour lithium trough.
- Review whether the current level is needed.Lower is kinder to the kidney. Use the lowest level that keeps the patient well.
- If the fall is sustained, involve nephrology.Send the eGFR series with dates, years on lithium, the usual trough, any toxicity episodes, and how well lithium has worked.
- Make the continue-or-stop decision with the patient, in writing.Record the reasons, the patient’s view, and what would change the decision.
| Weighs toward continuing | Weighs toward stopping or switching |
|---|---|
| A strong response to lithium, with serious relapses before it or when it was stopped | A sustained, steep decline despite a lower level and managed risk factors |
| A slow decline, or a fall explained by a reversible event | A partial response to lithium, with effective alternatives available |
| A stable eGFR at a lower level after adjustment | Repeated toxicity episodes despite good care |
| No acceptable alternative that has worked for this patient | eGFR approaching the range where reviews expect recovery after stopping to be less likely |
Is there a catch?
Three. The evidence is still split at low eGFR, stopping is itself a risky intervention, and heavy proteinuria is a different problem.
- The evidence at low eGFR is not settled.One study found the biggest benefit of stopping in patients with the lowest kidney function; reviews expect the least. Nobody should tell a patient with an eGFR in the 30s that stopping is pointless, or that it is certain to help.
- Stopping lithium is a psychiatric intervention.The Swedish authors themselves stress that kidney benefit must be weighed against relapse and suicide risk, and call for a patient-centred, not a kidney-centred, decision. If lithium is stopped, taper rather than stop abruptly, agree the replacement plan first, increase psychiatric review, and keep monitoring kidney function, because decline may continue for a time.
- Heavy proteinuria is not the typical lithium picture.The usual lesion is tubulointerstitial, and the urine is often unremarkable. The label does report nephrotic syndrome on lithium, with remission after stopping. New heavy proteinuria or oedema goes to nephrology promptly, with lithium named in the referral.
The full chapter is free to read — no membership needed.
Chapter 5 of Managing Mood Stabilizer Adverse Events gives you a two-minute bedside panel, a red, amber and green triage for a falling eGFR, the risk factors you can see coming, what slows the decline, the full continue-or-stop evidence, a patient counselling script and a copy-paste EMR note.
Read the Full Chapter →Table of contents
Chapters 1 and 5 are free to read. The rest are included with Academy membership. Members: open the course.
- 1Lithium Toxicity: Recognition, Severity and When to Send to the ED Free · read now
- 2Unexpected Lithium Levels: Interactions, Sick-Day Rules and Level Troubleshooting Members
- 3Neurologic Symptoms on Lithium: Toxicity, Encephalopathy, Serotonin Syndrome and NMS Members
- 4Lithium Polyuria and Nephrogenic Diabetes Insipidus Members
- 5Lithium and Declining Kidney Function: CKD, Proteinuria and When to Reconsider Treatment Free · read now
- 6Lithium Thyroid, Calcium and Parathyroid Abnormalities Members
- 7Lithium Tremor, Cognitive Effects, Weight Gain and Skin Problems Members
- 8Valproate Liver Injury, Pancreatitis and Serious Hypersensitivity: When to Stop Soon
- 9Valproate Hyperammonemia: When to Check Ammonia and When to Stop Soon
- 10Valproate Thrombocytopenia and Bleeding: CBC, Procedures and Dose Decisions Soon
- 11Valproate Weight Gain, Metabolic Effects and Hair Loss Soon
- 12Lamotrigine Rash: When to Stop and How to Recognize SJS/TEN and DRESS Soon
- 13Starting and Restarting Lamotrigine: Titration, Valproate and Missed Doses Soon
- 14Systemic Illness on Lamotrigine: HLH, Aseptic Meningitis and Blood Dyscrasias Soon
- 15Carbamazepine/Oxcarbazepine Rash: SJS/TEN, DRESS, HLA Testing and Cross-Reactivity Soon
- 16Carbamazepine/Oxcarbazepine Hyponatremia: When to Monitor, Reduce or Stop Soon
- 17Carbamazepine Blood and Liver Toxicity: When to Stop Soon
- 18Carbamazepine/Oxcarbazepine Drug Interactions: Induction, Autoinduction and Toxicity Soon
- 19Mood Stabilizers and Cardiac Conduction: Lithium, Lamotrigine and Other Sodium-Channel Blockers Soon
- 20Stopping Mood Stabilizers: Tapering and Reducing Recurrence Risk Soon
- 21Quick-Reference Monitoring and Management Grid Soon
Every chapter, every series, one membership.
Academy membership opens every chapter in this course and the rest of the Academy library, written for prescribers at the point of care.
See membership plans →

Responses