
FDA Approved Subcutaneous Olanzapine LAI: What Prescribers Need to Know vs. Zyprexa Relprevv

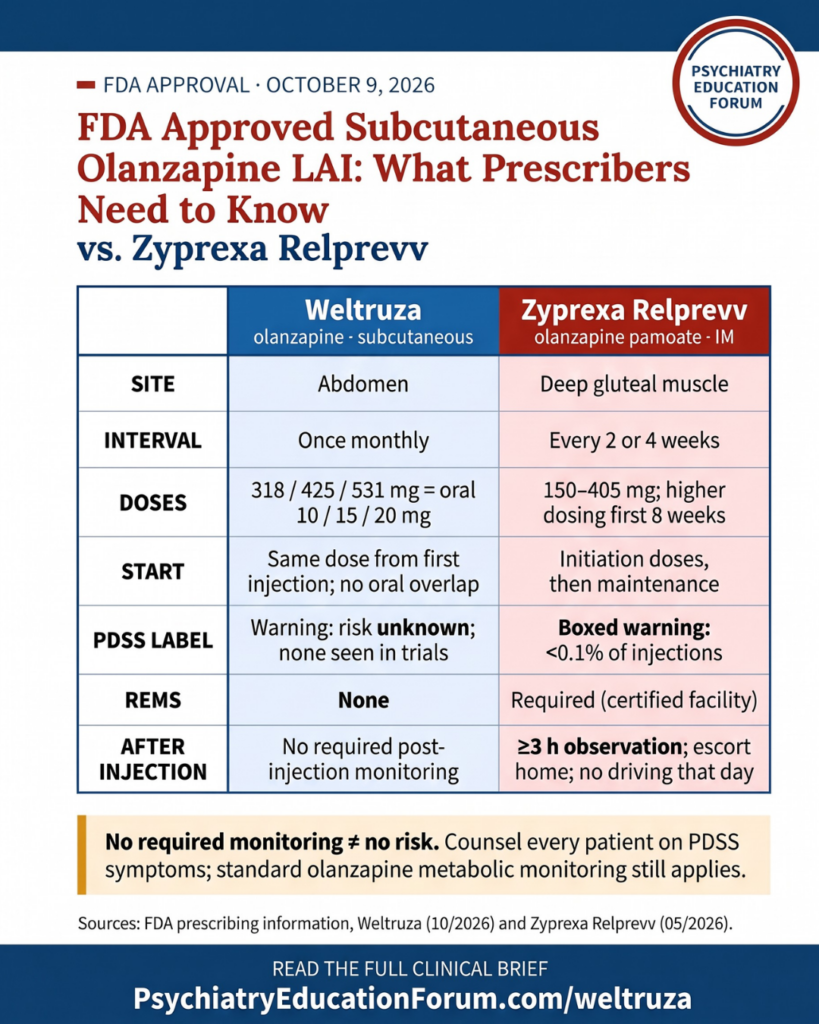
FDA Approved Subcutaneous Olanzapine LAI: What Prescribers Need to Know vs. Zyprexa Relprevv
Harvinder Singh, MD · Psychiatry Education Forum · October 9, 2026
New FDA approval · October 9, 2026For 17 years, long-acting olanzapine has meant a certified facility, a 3-hour observation period and an escort home. On October 9, 2026, the FDA approved Weltruza (Teva), a once-monthly subcutaneous olanzapine with none of those requirements. The catch: the label still carries a PDSS warning, and the risk is officially "currently unknown."
The 30-second version
- What changes: no REMS, no certified facility, no 3-hour observation, no loading dose, no oral overlap.
- What doesn't: a PDSS warning remains. No cases occurred in trials (3,971 injections), but the label calls the risk unknown.
- Dosing: 318 / 425 / 531 mg monthly into the abdomen = oral olanzapine 10 / 15 / 20 mg/day.
- Indication: schizophrenia in adults only. Unlike oral olanzapine, it is not approved for bipolar disorder.
- Evidence: one 8-week placebo-controlled acute trial (SOLARIS), bridged to oral olanzapine. No relapse-prevention or head-to-head trial.
- Availability: Teva expects US availability "in the coming weeks"; approval does not mean stock is on hand today.
1. Who is it for, and how do I start it?
Weltruza is approved for schizophrenia in adults. The most practical candidate is a patient who has benefited from and tolerated oral olanzapine 10–20 mg/day but would do better on a monthly injection because of adherence or preference.
That is a clinical selection strategy, not a label restriction. The label requires only that tolerability be established with oral olanzapine in patients who have not taken it before.
Swipe to see the full table →
| Oral olanzapine | Weltruza, once monthly | Injection volume |
|---|---|---|
| 10 mg/day | 318 mg | 0.9 mL |
| 15 mg/day | 425 mg | 1.2 mL |
| 20 mg/day | 531 mg | 1.5 mL |
- Olanzapine-naive? Establish tolerability with oral olanzapine first.
- Switching from oral? Give the first injection the next day. No loading dose and no oral supplementation.
- Administer: a healthcare professional injects it subcutaneously into the abdomen only.
Pharmacokinetics: median Tmax 11–14 days; median half-life 46.5 days; approximate steady state after the fourth dose. Adverse effects can therefore persist for weeks after an injection.
2. Is PDSS still a concern? Do I need to observe the patient?
No post-injection monitoring is required, but PDSS has not been ruled out. No required monitoring is not the same as no risk.
The label reports no PDSS cases in pre-marketing trials (849 patients, 3,971 injections), yet states the risk is "currently unknown."
Why the formulation may reduce PDSS risk (mechanistic rationale, not clinical proof). The copolymer depot is designed to resist dose dumping on contact with blood. In an in-vitro plasma test reported in the label, Weltruza released no quantifiable olanzapine at 1 and 3 hours and 8% at 24 hours. The intramuscular pamoate formulation released 50%, 63% and 91% at the same time points.
Why "zero cases" is not "no risk." No PDSS occurred across 3,971 injections in 849 patients. By the rule of three, the approximate upper 95% confidence bound is 0.076% per injection, assuming each injection is an independent event. Because patients received repeated injections, treat this as illustrative rather than a definitive bound.
Either way, the bound overlaps Relprevv's labeled rate of <0.1% of injections. The data do not establish that Weltruza's clinical PDSS risk is lower than Relprevv's. Larger postmarketing exposure will help characterize it.
In practice:
- Counsel on PDSS symptoms at each injection, as the label advises: excess sedation, confusion, ataxia, slurred speech, agitation, seizures.
- Tell patients to seek urgent care if these occur, including later the same day. With intramuscular olanzapine, PDSS has occurred more than 3 hours after injection.
- If signs of olanzapine overdose appear, include PDSS in the differential.
- Report any suspected case.
3. How is it different from Zyprexa Relprevv?
Same molecule, very different logistics: Weltruza fits an ordinary clinic visit, while Relprevv often takes half a day.
Swipe to see the full table →
| Weltruza (subcutaneous) | Zyprexa Relprevv (intramuscular) | |
|---|---|---|
| Formulation | Olanzapine in an in-situ copolymer depot | Olanzapine pamoate salt suspension |
| Site | Abdomen, 21-gauge needle | Deep gluteal IM, 19-gauge 1.5-inch needle |
| Interval | Every month | Every 2 or 4 weeks |
| Doses | 318 / 425 / 531 mg | 150–300 mg every 2 weeks or 300–405 mg every 4 weeks; higher dosing for the first 8 weeks |
| Oral tolerability first | Yes (if olanzapine-naive) | Yes |
| Initiation | Same dose from the first injection; no oral overlap | Higher initial dosing for 8 weeks, then a maintenance dose; oral supplementation generally not needed |
| PDSS labeling | Warning: risk unknown; none observed in trials | Boxed warning: <0.1% of injections, ~2% of patients |
| REMS | None | Yes: prescriber, facility, pharmacy and patient enrollment |
| Post-injection monitoring | Not required | ≥3 hours of continuous observation in a certified facility |
| After the visit | No restrictions beyond usual counseling | Must be accompanied home; no driving for the rest of the day |
| Half-life | ~46.5 days (median) | ~30 days |
| Pivotal efficacy evidence | One 8-week placebo-controlled trial | One 8-week placebo-controlled trial plus a 24-week maintenance trial |
Sources: Weltruza label (10/2026); Zyprexa Relprevv label (05/2026).
4. What side effects should I counsel on?
Expect oral olanzapine's systemic profile plus a new local one: injection-site reactions.
Swipe to see the full table →
| 8-week placebo-controlled period | Weltruza 318 / 425 / 531 mg | Placebo |
|---|---|---|
| Weight increased | 30% / 39% / 34% | 9% |
| Any injection-site reaction | 26% / 29% / 31% | 8% |
| Somnolence | 10% / 6% / 8% | 2% |
| Discontinuation for adverse reactions | 5% (all doses) | 4% |
"Weight increased" is the rate of reported adverse events, not the proportion with clinically significant (≥7%) weight gain. Source: Weltruza label, Tables 5 and 6.
- Injection-site reactions: mostly mild to moderate (induration 13%, pain 10%, erythema 10%). Six patients (1.2%) discontinued because of them, and 0.7% of injections caused a severe reaction.
- Metabolic: check fasting glucose and lipids at baseline and periodically, and monitor weight. In the SOLARIS open-label period, mean weight gain was 5.6 kg in patients treated 48 weeks or longer (n=137) Congress data
- Class warnings carried over from olanzapine: NMS, DRESS, tardive dyskinesia, orthostasis and falls, neutropenia, seizures, hyperprolactinemia, anticholinergic effects.
- Boxed warning: increased mortality in elderly patients with dementia-related psychosis.
5. Practical points for the clinic
Start preparing the kit before the patient arrives. The warm-up steps take about 45 minutes of elapsed, mostly hands-off time, and no 3-hour post-injection monitoring follows.
- Preparation: the kit is refrigerated and the diluent is solid when cold. Let the kit stand at room temperature for at least 30 minutes, then warm the diluent syringe in the supplied warming pack for at least 15 minutes. Skip the warming step if the kit has been at room temperature for more than 12 hours. An unopened kit can stay at room temperature for one period of up to 90 days.
- Injection: abdomen, at least 2 inches from the umbilicus. Avoid irritated, tattooed, scarred, hardened or stretch-marked skin.
- Missed dose: a dose can be given up to 1 week before or after it is due. If more than 5 weeks have passed since the last dose, give the next one as soon as possible and restart the monthly schedule from that date.
- CYP1A2 inhibitors (e.g., fluvoxamine): consider a lower dose. If 318 mg is not tolerated, switch to another olanzapine product at a lower dose.
- CYP1A2 or UGT inducers (e.g., carbamazepine, rifampin) and smoking: watch for loss of efficacy. Smokers had 22.5% higher clearance.
- Not studied: patients 65 or older; hepatic or renal impairment.
6. Is there a catch?
Yes: the convenience is proven; the long-term advantages are not.
- Relapse prevention: no randomized maintenance trial. Long-term data are open-label only.
- Head-to-head comparisons: none versus oral olanzapine, Relprevv or other LAIs.
- Real-world PDSS rate: not yet known (see section 2).
- Generalizability: SOLARIS enrolled acutely ill adults aged 18–64 (68% Black, 75% male, median age 44). Elderly, first-episode and medically complex patients were not studied.
- Peer review: at the time of writing, I could not identify a full peer-reviewed publication of the SOLARIS phase 3 results. The available efficacy data are reported in the FDA prescribing information and conference presentations.
7. The evidence: SOLARIS in brief
All three doses beat placebo by about 10–11 PANSS points at week 8.
Design. Phase 3, multinational, randomized, double-blind (NCT05693935). In period 1, 675 adults with an acute exacerbation (PANSS 80–120, CGI-S ≥4) were randomized 1:1:1:1 to 318, 425 or 531 mg or placebo, given as two monthly injections over 8 weeks. Period 2 was an open-label safety extension of up to 48 weeks, in which placebo patients were re-randomized to active doses.
Swipe to see the full table →
| Arm | N | PANSS change at week 8 | Difference vs placebo (95% CI) |
|---|---|---|---|
| Placebo | 165 | −12.17 | — |
| 318 mg | 163 | −21.91 | −9.75 (−13.60 to −5.89) |
| 425 mg | 166 | −23.44 | −11.27 (−15.01 to −7.53) |
| 531 mg | 165 | −21.93 | −9.76 (−13.50 to −6.02) |
Mean baseline PANSS 95.8. Source: Weltruza label, Table 10.
- Secondary endpoints: CGI-S and PSP (personal and social functioning) also improved significantly versus placebo at week 8.
- Onset: separation on PANSS by week 2 (318 and 425 mg) or week 3 (531 mg) Congress data
- Dose–response: no clear dose–response gradient was demonstrated in the 8-week trial.
- Long term (open-label): improvements in PANSS, CGI-S and PSP were generally sustained in patients who continued for up to 48 weeks, with no PDSS events reported. Without a randomized comparator, this does not establish relapse prevention.
How to read it: this is an acute efficacy trial against placebo, not a maintenance trial. The approval also relies on the established efficacy of oral olanzapine.
Go deeper with PEF Academy
Point-of-care psychopharmacology chapters written for busy prescribers, including antipsychotic use in pregnancy, breastfeeding and medical conditions.
See membership optionsReferences
- FDA label Weltruza (olanzapine) for extended-release injectable suspension, Prescribing Information. Teva Neuroscience; revised 10/2026.
- FDA label Zyprexa Relprevv (olanzapine) Prescribing Information. Eli Lilly; revised 05/2026.
- Press release Teva announces FDA approval of Weltruza. October 9, 2026.
- Congress poster Correll C, et al. Efficacy of TV-44749 in schizophrenia: SOLARIS phase 3 results. Not peer-reviewed.
- Congress poster Early, consistent symptom improvement with TV-44749 through week 8: SOLARIS. Not peer-reviewed.
- Company release Medincell: long-term SOLARIS safety and weight data, Psych Congress 2025.
Disclaimer: This article is for educational purposes for licensed healthcare professionals and is not a substitute for clinical judgment or the full prescribing information. Verify dosing and safety details against the current FDA label before prescribing.



Responses