
Can a patient be lithium-toxic with a “normal” level?

Can a Patient Be Lithium-Toxic With a “Normal” Level — and Why Does the Number Mislead?
A family member calls: she is unsteady, her speech is slurred, and she “isn’t making sense.” The level comes back only a little above target, or even inside it. The reflex answer is that the number is fine, so the problem must be something else, or a small dose adjustment by phone will do. That reflex is how chronic lithium toxicity gets missed. The level is a number drawn from a vein at one moment. Toxicity is what is happening in the brain, and the brain takes lithium up slowly and gives it back slowly.
The 30-second version
- Yes, it happens. The US lithium label warns that some patients show toxic signs at concentrations within the therapeutic range.
- Chronic toxicity is the trap. The brain has caught up with the serum, so neurotoxicity can sit alongside a level that looks only modestly raised. It carries the highest neurotoxicity risk of the three presentations.
- A level without times is half a result. Without the time of the last dose and the time of the draw, you cannot compare it with previous troughs.
- Grade the patient, not the printout. The classic severity grading for lithium intoxication contains no lithium concentration at all.
- Any new neurological sign means the emergency department, whatever the level. Coarse tremor, unsteadiness, slurred speech or confusion are the signs.
- A falling level does not end the episode. Neurological recovery lags the number, and in a minority of patients it never completes.
Can a patient really be toxic at a level in the therapeutic range?
Yes. The US label says so directly: some patients abnormally sensitive to lithium show toxic signs at concentrations considered within the therapeutic range.
| US label number | Concentration | What it does not tell you |
|---|---|---|
| Acute treatment target | 0.8–1.2 mEq/L | Whether the brain has caught up. These are serum numbers, and they sit close together. |
| Maintenance target | 0.8–1.0 mEq/L | |
| Called toxic | ≥1.5 mEq/L |
Lithium is a small ion, not bound to protein, that distributes first through extracellular fluid and only then, slowly, into cells, including neurons. Brain lithium lags serum lithium on the way up and lags it again on the way down. That lag is the whole story.
So a level in range with new neurological signs is not reassurance. It is a reason to look harder: for accumulation the number has not yet caught, and for a second drug, because lithium combined with an antipsychotic or a serotonergic drug can cause trouble the level says nothing about.
Why is chronic toxicity the dangerous one?
Because the brain has had time to equilibrate with the serum, so the number understates the damage that is already happening.
Toxicology reviews separate lithium poisoning into three presentations because they differ in where the lithium is when you draw the level.
| Presentation | Who | What the level tells you | Neurotoxicity risk |
|---|---|---|---|
| Acute | Lithium-naive patient, single large ingestion | A high early level may overstate current brain exposure, but can understate the eventual peak with sustained-release tablets | Lowest |
| Acute-on-chronic | Patient on maintenance lithium who takes an extra large amount | A high level on top of an already loaded brain | Intermediate |
| Chronic | Patient on a stable dose whose lithium elimination has fallen | Understates severity: neurotoxicity can be marked at a modestly raised level | Highest |
Chronic toxicity is the one psychiatric prescribers meet most often. Nobody has overdosed and the dose has not changed. Elimination has fallen, almost always for one of these reasons:
| What changed | How it raises lithium |
|---|---|
| Vomiting, diarrhoea, fever, poor intake | Volume and sodium depletion make the kidney reabsorb more sodium, and lithium with it. It keeps acting while you wait. |
| A new ACE inhibitor, ARB or diuretic | The kidney holds on to sodium and filters less. The label lists all of these as interactions. |
| Regular NSAIDs, including over-the-counter ibuprofen | Reduced renal lithium clearance; worst combined with one of the drugs above. |
| Falling kidney function | Removes the main route out. Toxicity keeps worsening until clearance recovers. |
Lowest risk does not mean safe to manage by phone. Every intentional or sustained-release ingestion still goes to the emergency department.
What is wrong with the level I already have?
Usually its timing. A level without the time of the last dose and the time of the draw cannot be compared with anything.
Maintenance monitoring is built on a trough drawn about twelve hours after the last dose, immediately before the next one. In suspected toxicity the question changes: how much lithium is on board, is it still rising, and is elimination working? One level answers none of those well. Four ways the number misleads:
| Pitfall | What happens | What to do |
|---|---|---|
| Random timing | A level drawn soon after a dose reads higher than the trough | Record the time of the last dose and the draw on every result; compare like with like |
| Sustained-release overdose | Absorption continues for hours; an early level can sit well below the eventual peak | Never accept a single early level; the emergency department should trend it |
| Chronic toxicity, modest level | Neurotoxicity established at a level that looks only a little high | Act on the neurological examination, not the number |
| Falling level, persisting symptoms | Brain lithium leaves more slowly than serum lithium | Expect recovery to lag; a normalising number does not end observation |
If not the level, what tells me how sick the patient is?
The neurological examination. The widely cited clinical grading of lithium intoxication grades severity by neurological state and contains no lithium concentration.
The grading comes from a 1978 case series, as reproduced in a later toxicology review. Use it as a shared vocabulary for urgency, not a validated prognostic score.
| Grade | Clinical picture (paraphrased) | What it means for you |
|---|---|---|
| Mild | Nausea, vomiting, tremor, hyperreflexia, agitation, muscle weakness, ataxia | New neurological signs: already beyond a phone dose adjustment |
| Moderate | Stupor, rigidity, hypertonia, hypotension | Emergency department now |
| Severe | Coma, seizures, myoclonus, cardiovascular collapse | Emergency services |
The change you are listening for is a shift in character. A fine hand tremor is common on therapeutic lithium. Toxicity turns it coarse and adds unsteadiness, slurring and slowing. Families describe it in ordinary words: “wobbly,” “drunk,” “not herself,” “can’t hold a cup.”
So when does the patient go to the emergency department?
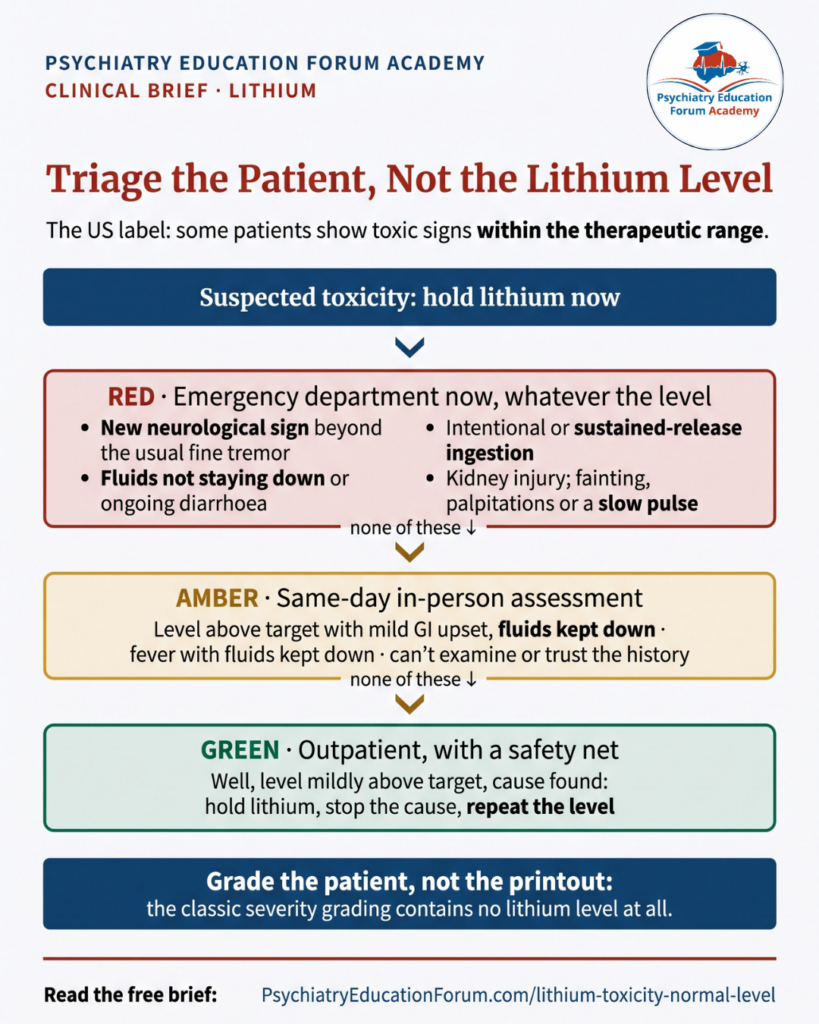
On the clinical picture, not the number. Hold the next dose, ask five questions, and triage the patient red, amber or green.
- Is the tremor different from usual?Bigger movements, worse when reaching, spilling drinks, now in the legs or jaw.
- Unsteady, slurred or confused?Any of these is a new neurological sign, whatever the level.
- Vomiting or diarrhoea, and can they keep fluids down?Fluid loss drives accumulation, and it keeps acting while you wait.
- Any new medicine, or fever?Name them: blood pressure tablets, water tablets, anti-inflammatories bought over the counter.
- Could they have taken extra, and which tablets?Any intentional or sustained-release ingestion goes to the emergency department.
| Triage | If any of these | Why |
|---|---|---|
| Red: ED now | Any new neurological sign beyond the usual fine tremor | Chronic toxicity demands it: the number may never look frightening enough |
| Red: ED now | Any intentional or sustained-release ingestion, however well the patient looks | Absorption can continue for hours; a modest early level is not a safe discharge |
| Red: ED now | Fluids not staying down, or ongoing diarrhoea; known or suspected kidney injury | Accumulation keeps going while you wait |
| Red: ED now | Fainting, palpitations or a slow pulse | Lithium affects cardiac conduction; the patient needs an ECG |
| Red: ED now | Rigidity with fever, or clonus with agitation, on an antipsychotic or serotonergic drug | The label warns of an encephalopathic syndrome with antipsychotics and of serotonin syndrome |
| Amber: same day | Recent interacting drug plus any illness; you cannot examine the patient or trust the history; an older patient living alone | Too much uncertainty to manage by phone |
Two things not to do while you arrange it. Do not tell the patient to drink large volumes of water to “flush it out”: free water does not correct sodium depletion and can worsen low sodium. And do not add or increase a diuretic. Send the emergency team what they need: the formulation, the time of the last dose and of the draw, any sustained-release ingestion, baseline kidney function, any history of heavy urination, and every interacting drug started recently.
Is there a catch?
Two. The level still matters for some decisions, and recovery does not follow it.
- The level is not useless.It still informs the emergency and nephrology teams’ decision about extracorporeal removal, alongside kidney function and the neurological state. There is no single agreed severity score and no guideline outpatient cut-off; we have not merged them, because that would claim a consensus that does not exist.
- Recovery does not follow the number.Neurological recovery lags the fall in the level, sometimes by days. A minority of patients are left with persistent deficits, most often cerebellar: unsteadiness, tremor and slurred speech that do not resolve when the number does. That is why chronic toxicity with neurological signs is an emergency, not a dose problem.
The full chapter is free to read — no membership needed.
Chapter 1 of Managing Mood Stabilizer Adverse Events gives you a two-minute bedside panel, phone triage in red, amber and green, the risk factors that drive chronic toxicity, what the emergency department will do, the restart decision after recovery, a family counselling script and a copy-paste EMR note.
Read the Full Chapter →Table of contents
Chapter 1 is free to read. The rest are included with Academy membership.
- 1Lithium Toxicity: Recognition, Severity and When to Send to the ED Free · read now
- 2Unexpected Lithium Levels: Interactions, Sick-Day Rules and Level Troubleshooting Members
- 3Neurologic Symptoms on Lithium: Toxicity, Encephalopathy, Serotonin Syndrome and NMS Members
- 4Lithium Polyuria and Nephrogenic Diabetes Insipidus Soon
- 5Lithium and Declining Kidney Function: CKD, Proteinuria and When to Reconsider Treatment Soon
- 6Lithium Thyroid, Calcium and Parathyroid Abnormalities Soon
- 7Lithium Tremor, Cognitive Effects, Weight Gain and Skin Problems Soon
- 8Valproate Liver Injury, Pancreatitis and Serious Hypersensitivity: When to Stop Soon
- 9Valproate Hyperammonemia: When to Check Ammonia and When to Stop Soon
- 10Valproate Thrombocytopenia and Bleeding: CBC, Procedures and Dose Decisions Soon
- 11Valproate Weight Gain, Metabolic Effects and Hair Loss Soon
- 12Lamotrigine Rash: When to Stop and How to Recognize SJS/TEN and DRESS Soon
- 13Starting and Restarting Lamotrigine: Titration, Valproate and Missed Doses Soon
- 14Systemic Illness on Lamotrigine: HLH, Aseptic Meningitis and Blood Dyscrasias Soon
- 15Carbamazepine/Oxcarbazepine Rash: SJS/TEN, DRESS, HLA Testing and Cross-Reactivity Soon
- 16Carbamazepine/Oxcarbazepine Hyponatremia: When to Monitor, Reduce or Stop Soon
- 17Carbamazepine Blood and Liver Toxicity: When to Stop Soon
- 18Carbamazepine/Oxcarbazepine Drug Interactions: Induction, Autoinduction and Toxicity Soon
- 19Mood Stabilizers and Cardiac Conduction: Lithium, Lamotrigine and Other Sodium-Channel Blockers Soon
- 20Stopping Mood Stabilizers: Tapering and Reducing Recurrence Risk Soon
- 21Quick-Reference Monitoring and Management Grid Soon
Every chapter, every series, one membership.
Academy membership opens every chapter in this course and the rest of the Academy library, written for prescribers at the point of care.
See membership plans →