
Does valproate prevent readmission better than lithium after first mania?

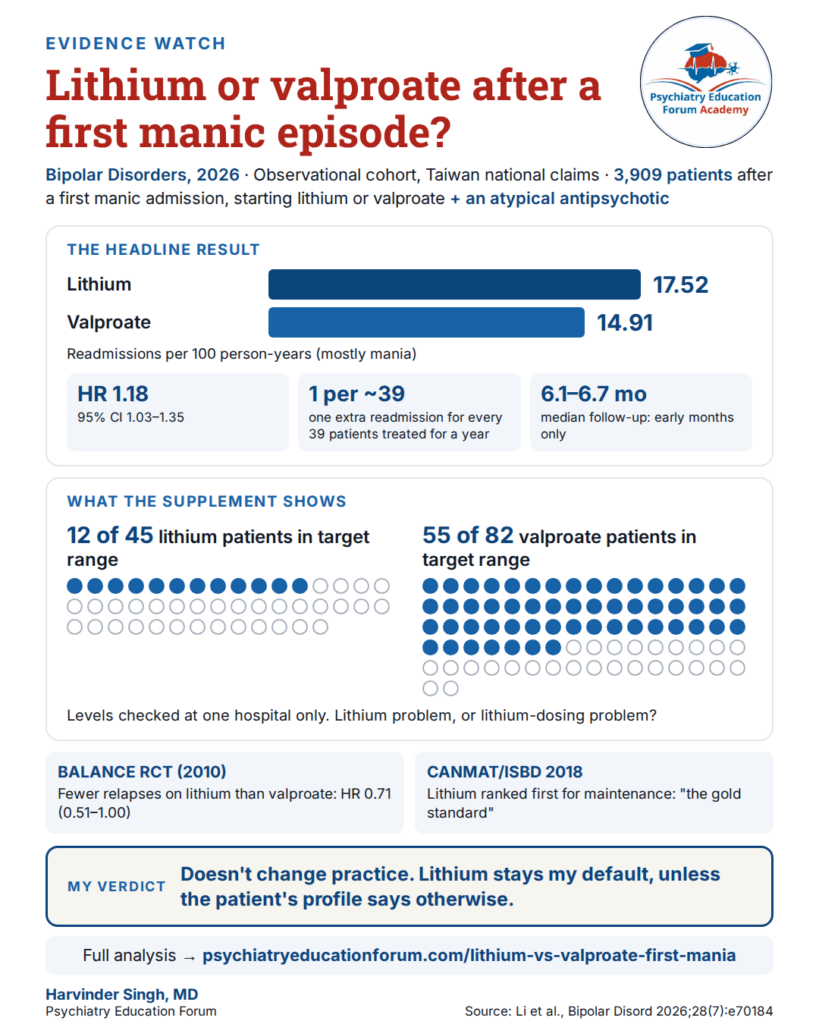
Lithium or valproate after a first manic episode?
A new Taiwanese cohort found more readmissions on lithium. The detail in its supplement changes how to read that result.
Harvinder Singh, MD · Board-certified psychiatrist · Psychiatry Education Forum
- Source
- Peer-reviewed (Bipolar Disorders, 2026), plus the authors' supplement
- Design
- Observational, propensity-matched cohort (Taiwan national insurance claims)
- Absolute numbers
- Reported in the supplement only
- Applies if
- Your patient was just discharged after a first manic admission and is starting lithium or valproate with an atypical antipsychotic
- Verdict
- Doesn't change practice. Lithium dosing in this study leaves the comparison unresolved.
1The finding in one line
After a first manic admission, patients started on lithium plus an atypical antipsychotic were rehospitalised more often than those started on valproate plus an atypical antipsychotic, at least in the first months of treatment.
2Who this is about, and who it isn't
About
| Patients | 3,909 patients; mean age 42.4; 42.9% male |
|---|---|
| Index event | First hospitalisation for mania (bipolar I) |
| Treatment | Lithium or valproate, each with an atypical antipsychotic |
| Timing | Started within 30 days of discharge |
| Data | Taiwan national insurance claims, 2011–2022 |
| Excluded | Schizophrenia, schizoaffective disorder, dementia |
Not about
| Monotherapy | Lithium or valproate without an antipsychotic |
|---|---|
| Later episodes | Patients past their first manic admission |
| No mania admission | Anyone never hospitalised for mania |
If that's your patient, you can stop here.
3The numbers, made usable
Two things to keep in mind:
- This covers the early months only. Median follow-up was 6.1 months on lithium and 6.7 months on valproate. Patients stopped being counted once they stopped or switched their drug, which happened to 52.4% and 59.5% of them.
- It held up across the authors' checks. All 12 sensitivity analyses gave hazard ratios between 1.16 and 1.31, including intention-to-treat (1.31) and adjustment for adherence (1.17).
4The detail the abstract leaves out
The national data contain no drug levels. The authors checked one hospital's records (45 lithium patients, 82 valproate patients) to see whether levels were in target range during the first manic admission.
When they adjusted for this in that small group, lithium still looked worse (HR 1.52), but the confidence interval ran from 0.56 to 4.16. The group was too small to settle the question either way. So it remains open whether this is a lithium problem or a lithium-dosing problem.
5How this fits the existing evidence
The authors point out the gap themselves:
"No randomized trials have directly compared these regimens in early-course illness."
The closest randomised evidence points the other way. BALANCE (Lancet, 2010) randomly assigned 330 people aged 16 and over with bipolar I disorder to lithium, valproate, or both, open-label, for up to 24 months. A relapse needing new treatment occurred in 65 of 110 on lithium (59%) and 76 of 110 on valproate (69%). Unlike the Taiwan study, neither arm received an antipsychotic.
- Patients with no previous maintenance treatment in BALANCE, the group closest to a first episode, showed no lithium advantage (HR 1.13). The subgroup was small, and the difference between subgroups wasn't statistically significant.
- Lithium dosing fell short in the trial too. 66 of 110 lithium patients reached the trial's minimum dose, compared with 108 of 110 on valproate.
| Source | Type | What it says about lithium vs valproate |
|---|---|---|
| Li et al. 2026 | Observational cohort | More readmissions on lithium + antipsychotic in the early months; lithium levels mostly below range where checked |
| BALANCE 2010 | Randomised trial | Fewer relapses on lithium monotherapy over up to 24 months |
| CANMAT/ISBD 2018 | Guideline | Both first-line for maintenance; lithium ranked first and called "the gold standard for maintenance treatment" |
CANMAT/ISBD 2018, its most recent bipolar guideline, recommends "that agents listed higher in the hierarchy be tried first, unless there are patient-specific reasons for choosing an agent lower in the order."
6What the authors concluded vs. what the data support
The authors conclude that the results suggest "potential early-phase maintenance advantages of valproate combinations over lithium combinations."
Their own supplement complicates that. In the only subset where levels were checked, 12 of 45 lithium patients were in target range, compared with 55 of 82 on valproate, and the abstract doesn't mention it. That doesn't prove lithium dosing explains the result. It does mean the study may be comparing under-dosed lithium with adequately dosed valproate.
7What it doesn't answer
- Would the gap remain if lithium were dosed properly? In the one subset where levels were checked, 12 of 45 lithium patients were in range. The national data can't answer this.
- What happens after the first months? Median follow-up was 6.1 vs 6.7 months. The case for lithium rests on long-term maintenance, which this study doesn't measure.
- Suicide. The authors charted suicide-related events in their supplement but report no figures that can be checked.
Does this change practice?
No. Lithium remains my default for bipolar disorder, unless something in the patient's overall profile gives a reason to choose a different mood stabiliser.
The difference in this study is real, and it held up in every analysis the authors ran. But in the one place they could check, most lithium patients weren't in target range. I suspect that, more than lithium itself, is why valproate came out ahead. The one randomised trial comparing the two drugs favoured lithium, and CANMAT/ISBD 2018 calls lithium "the gold standard for maintenance treatment" and ranks it first.
This study raises a fair question but doesn't answer it. A comparison with confirmed therapeutic lithium levels would.
What I'm doing differently: nothing changes in my prescribing. Lithium stays my first choice, with the choice still shaped by each patient's full profile.
Become an Academy member
Full access to every course and Rapid Decision Guide, including the Bipolar Disorder course.
Sources
- Li PY, Wang MT, Jeng JS, et al. Comparative effectiveness of lithium- vs. valproate-based combinations with atypical antipsychotics in preventing rehospitalization after a first manic episode of bipolar I disorder. Bipolar Disorders. 2026;28(7):e70184. doi.org/10.1111/bdi.70184. Observational cohort. The supplement (Tables S2, S4, S6) is free to download from the article page. The authors declare no conflicts of interest.
- BALANCE investigators; Geddes JR, Goodwin GM, et al. Lithium plus valproate combination therapy versus monotherapy for relapse prevention in bipolar I disorder (BALANCE). Lancet. 2010;375:385–95. PMID 20092882. Randomised controlled trial. Funded by the Stanley Medical Research Institute and Sanofi-Aventis.
- Yatham LN, Kennedy SH, Parikh SV, et al. CANMAT and ISBD 2018 guidelines for the management of patients with bipolar disorder. Bipolar Disorders. 2018;20:97–170. doi.org/10.1111/bdi.12609. Guideline.


Responses