
Do antidepressants really blunt emotions in half of patients?

Do antidepressants really blunt emotions in half of patients?
And why the number everyone quotes cannot tell you whether the drug did it.
A patient tells you the tablets have flattened her. She has stopped crying. She watches her children and feels, in her words, nothing behind it. She has read that this happens to about half of people on antidepressants, and she wants to stop.
The figure she read is real and it is published. It is also the answer to a different question from the one she is asking — and the study that comes closest to her actual question points the other way.
The 30-second version
- The 46% figure comes from an uncontrolled internet survey of treated patients. There was no untreated-depressed comparison group.
- The questionnaire it used correlates with a depression rating scale at r = 0.521 — so a high score is also what an under-treated patient produces.
- In randomised trials, emotional responsiveness improved on average and worsened in 6% or fewer. Within the placebo-controlled portion, no drug differed from placebo.
- No study in a non-depressed population has shown blunting attributable to the drug. That study has not been done.
- So the first question is not which drug to switch to. It is whether the depression is fully treated.
- Apathy without sadness is a different presentation, and in an older adult it may be the first sign of something other than a drug effect.
- Lowering the dose to reverse blunting is supported by case reports, not trials. Worth trying. Not worth promising.
Where does the 46% figure come from?
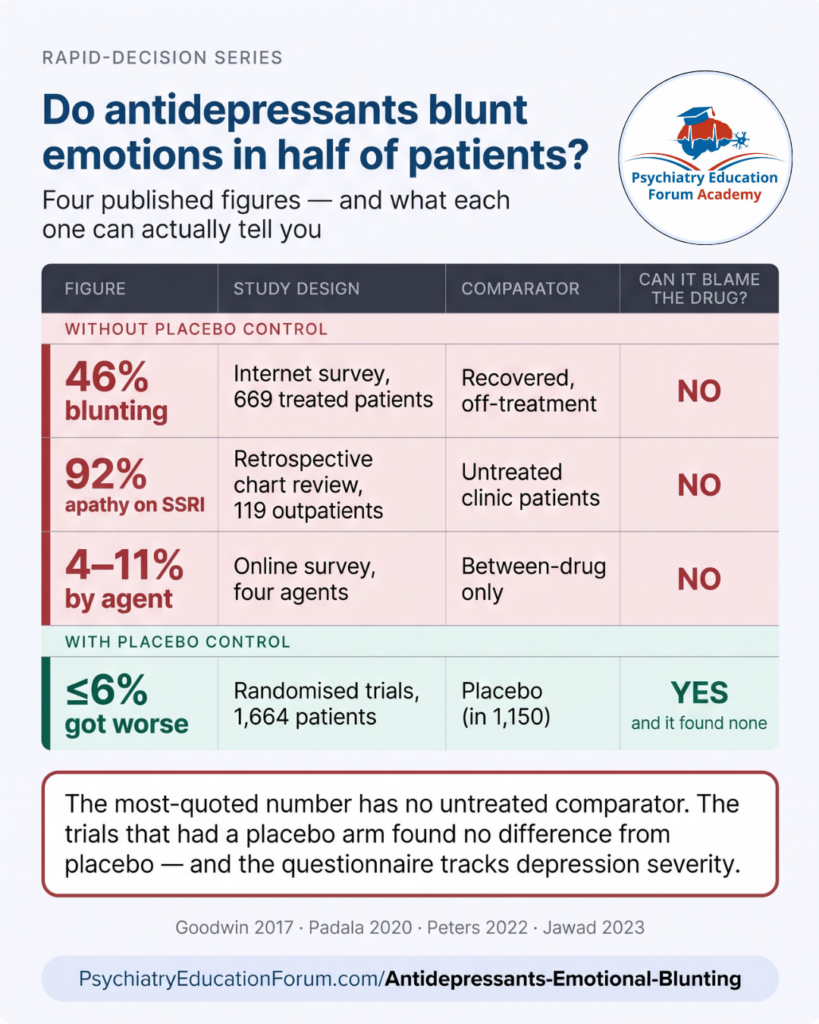
The source is a 2017 survey of 669 patients on antidepressants, alongside 150 people who had recovered and come off treatment. Blunting was reported by 46% of the treated group, whose questionnaire score averaged 42.8 against 25.7 in the recovered controls.
Look at what that design can and cannot support. It compares treated-and-still-unwell patients against recovered-and-untreated ones. Those two groups differ in two ways at once — whether they are on a drug, and whether they are still depressed. The study cannot separate them.
The comparison it would have needed is the one it did not have: depressed patients taking nothing.
| Figure | Design and population | Comparator | Can it blame the drug? |
|---|---|---|---|
| 46% blunting | Internet survey, 669 treated patients | Recovered, off-treatment controls | No — the two groups differ in illness as well as in treatment |
| 92% apathy | Retrospective chart review, 119 outpatients | Untreated clinic patients, not remitted | No — confounding by indication is unaddressed |
| 4.1–10.7% by agent | Online survey of users of four antidepressants | Between-drug only | No — and these should not be used to rank agents |
| ≤6% worsened | Three randomised trials, 1,664 patients | Placebo, in 1,150 of them | Yes — and it found no difference from placebo |
What did the placebo-controlled trials show?
A secondary analysis pooled three randomised trials — 1,664 patients in total, of whom 1,150 were in trials carrying a placebo arm. Emotional responsiveness improved in every arm. Worsening occurred in 6% or fewer. No active drug differed from placebo, and the relationship between blunting and outcome was near-identical in the placebo group.
One limit worth stating, because it cuts against the reassurance. The third trial in that analysis compared escitalopram against bupropion with no placebo arm. So "no difference from placebo" is demonstrated in 1,150 patients, not all 1,664, and escitalopram specifically has never been tested against placebo for this outcome.
So is it the drug or the depression?
The design that would settle this is straightforward to describe: give antidepressants to people who are not depressed, and see whether they report emotional blunting. It has not been adequately done. The scoping reviewers name this absence directly, and describe the literature as severely limited in separating blunting from pre-treatment depression.
What exists instead points in an uncomfortable direction for the popular version of this story.
- The placebo-controlled data argue against a drug effect. Improvement in every arm, ≤6% worsening, no separation from placebo in acute treatment.
- Healthy-volunteer work does not close the gap. Single doses alter emotional processing on laboratory tasks. But the largest imaging trial at a realistic duration — escitalopram 20 mg versus placebo for three to five weeks — found no amygdala effect. These are task endpoints, not the clinical complaint.
- Dose-response is case-level. Reported in case series, flagged by the authors themselves as hypothesis-generating.
- The one randomised between-drug signal is small and contested in its meaning. Agomelatine against escitalopram over 24 weeks: 28% versus 60% endorsing reduced emotional intensity, in a questionnaire subgroup of 45 patients. The trial authors concluded agomelatine has a real advantage; later reviewers read the same result as a depression symptom the main rating scale failed to capture. Two of the trial’s authors work for the company that makes agomelatine.
What this does not mean
It does not mean your patient is wrong, and it does not mean nothing is happening to her. People describe numbness as something distinct from their depression, and they are reporting a real experience.
What the evidence cannot currently do is attribute it. That changes the first move rather than the diagnosis: before asking which drug to switch to, ask whether the depression is actually in remission — because unresolved depression produces exactly this presentation, and it is the explanation you can do something about today.
Can any test tell them apart?
The Oxford questionnaire, the standard instrument in this field, was built from patient interviews and correlates with the depression subscale of the Hospital Anxiety and Depression scale at r = 0.521. Its own developers concluded that blunting cannot be described simply as a side effect of antidepressants, but also as a symptom of depression.
That is close to circular for the purpose the score gets used for. A high score is what you would expect from a patient whose depression is not fully treated, whether or not they are taking anything. The scoping reviewers put it plainly: the instrument measures blunting but cannot separate residual anhedonia from a drug effect, and it rests on the patient's own attribution.
Is blunting the same thing as apathy?
Ask whether there is sadness. Depression has it. Apathy does not.
This matters more than the terminology suggests. Across neurocognitive disorders, apathy and depression are uncorrelated, neither predicts the other, they have distinct anatomy, and they respond to different treatments. Apathy is also the most common neuropsychiatric symptom of Alzheimer disease, and antidepressants are largely ineffective against it.
| Depression | Apathy | |
|---|---|---|
| Sadness | Present | Absent |
| What is lost | Mood, pleasure, hope | Motivation and initiation |
| Patient says | “I feel awful.” | “I just don’t start anything.” |
| Responds to antidepressants | Yes | Largely not |
So an older adult who becomes unmotivated on an SSRI presents three possibilities at once — residual depression, a drug-associated apathy syndrome, or early neurodegenerative disease. Increasing the antidepressant is the wrong move for two of the three.
Does lowering the dose fix it?
Reversal after dose reduction or discontinuation is reported across several uncontrolled case series, including a six-case series in which apathy scores improved after stopping an SSRI — only one of which had a pre-treatment score to compare against. There is no controlled reversal trial.
That does not make dose reduction unreasonable. It makes it a reasonable thing to try while saying what you know. If it works you have not proven the drug was the cause; if it does not, you have not excluded it.
One trap to avoid. Emotional blunting also occurs as a withdrawal phenomenon when antidepressants are stopped — and how common discontinuation symptoms are is itself disputed — the most-cited systematic review put it at 56%, an estimate challenged on methodological grounds, with later meta-analyses reporting substantially lower figures once nocebo effects are separated out, and those in turn contested by reanalysis. A patient who becomes flat two weeks after a taper is a different problem from one who became flat while stable on treatment, and the two get conflated constantly.
Should you switch to vortioxetine?
The vortioxetine blunting data come from a switch programme in patients with an inadequate response to an SSRI or SNRI: questionnaire scores improved by 29.8 points in 143 patients, and half no longer reported blunting. A Spanish subgroup of 67 reported 70.4% blunting-free.
Those are large effects. They are also open-label, single-arm, without any blinded comparator, confounded by the fact that the patients' depression was improving at the same time, and sponsored by the manufacturer.
The cognitive claim is on firmer ground but smaller than marketed. Across three randomised trials the effect on the digit symbol test was 0.35 before adjusting for depression score and 0.24 after — so roughly a third of the apparent benefit travels through mood. A 2025 network meta-analysis found vortioxetine was the only antidepressant to separate from placebo on cognition at all, at effect sizes between 0.23 and 0.29, while escitalopram, citalopram, paroxetine and fluoxetine did not differ from placebo.
The honest caveat
Both switch targets have the same problem from opposite directions. Agomelatine has randomisation and blinding, on a subgroup of 45, in a trial co-authored by employees of the company that makes it. Vortioxetine has a larger effect and more patients, in a design with no comparator, also run by its manufacturer.
Neither supports telling a patient that a particular agent will fix this. What you can honestly say is that switching is reasonable to try, and that the evidence for any specific target is weak.
So what do you actually do?
- Ask whether there is sadness. Flat with low mood, guilt and loss of pleasure is depression. Flat without sadness is apathy. They go different directions from here.
- Score the depression. Blunting tracks residual severity. A patient who feels nothing at a PHQ-9 of 12 is under-treated until proven otherwise — and this is the step that gets skipped, because the patient has already framed the problem as a drug effect.
- Check onset and fluctuation in an older patient. Acute onset with fluctuating attention is hypoactive delirium and needs a medical workup that day, not a medication review.
- Audit anticholinergic burden. Paroxetine and the tricyclics, plus everything else they take. This is the one place where the drug-attribution evidence is actually solid.
- Reduce the dose if you like, and say what you know. Case-level evidence. Reasonable to try. Not a promise.
- Consider behavioural activation before another drug. It has the strongest evidence of anything here for depression broadly, targets exactly the loss of positive reinforcement these patients describe, and carries no pharmacological risk.
And tell the patient not to stop on her own. Stopping abruptly produces its own version of numbness, plus the risk of relapse — after which nobody will be able to tell which was which.
The free chapter below carries the full differential, the anticholinergic detail, the dementia-risk evidence, a copy-paste EMR note, and a counselling script for exactly this conversation.
Emotional Blunting, Apathy & Cognitive Effects
The full chapter — four constructs separated, the attribution evidence laid out, the differential including delirium and early neurodegenerative disease, the management ladder, a copy-paste EMR note, and how to have this conversation without overpromising.
Read the full chapter free →The complete series
Thirty-one point-of-care chapters across seven parts, publishing through September. Every chapter opens with the bottom line, works the differential, and closes with an action ladder, a counselling script, and a copy-paste EMR note.
- 1Serotonin SyndromeMembers
- 2Activation Syndrome & Treatment-Emergent SuicidalityMembers
- 3Antidepressant-Induced AkathisiaMembers
- 4Treatment-Emergent Mania & the Bipolar SwitchFree
- 5Tremor & MyoclonusMembers
- 6Bruxism & Jaw ClenchingMembers
- 7Dystonia, Parkinsonism & Tardive DyskinesiaMembers
- 8Nausea, Dyspepsia, Diarrhea & Dry MouthMembers
- 9Insomnia, Vivid Dreams & REM Sleep EffectsMembers
- 10Sedation & Daytime SomnolenceMembers
- 11Emotional Blunting, Apathy & Cognitive EffectsFree
- 12Weight Gain & Appetite ChangeMembers
- 13Sexual Dysfunction & PSSDMembers
- 14Falls, Fractures & Bone HealthMembers
- 15QTc Prolongation, Tachycardia & Cardiac ConductionMembers
- 16SNRI-Associated HypertensionMembers
- 17Orthostatic Hypotension & DizzinessMembers
- 18Antidepressant-Induced Excessive SweatingMembers
- 19Urinary Retention & IncontinenceMembers
- 20Bleeding Risk: GI, Perioperative & AnticoagulantMembers
- 21Hyponatremia & SIADHMembers
- 22Transaminitis & Drug-Induced Liver InjuryMembers
- 23Discontinuation Syndrome & Hyperbolic TaperingMembers
- 24Switching & Cross-Taper SafetyMembers
- 25The Bupropion Set: Seizure Risk & Lowered Seizure ThresholdMembers
- 26The Mirtazapine Set: Sedation, Appetite & Rare NeutropeniaMembers
- 27The Serotonin Modulator Set: Trazodone, Vilazodone & VortioxetineMembers
- 28The TCA Set: Anticholinergic Burden, Conduction Delay & Overdose LethalityMembers
- 29The MAOI Set: Hypertensive Crisis, Tyramine & Washout WindowsMembers
- 30Rare but Serious: Angle-Closure Glaucoma, SJS/TEN, Blood DyscrasiasMembers
- 31Quick-Reference Matrix: Antidepressant Adverse Event GridMembers
Join the Academy
One membership covers this series and the entire Academy library — psychopharmacology lessons, case discussions and clinical pearls, with new content added monthly.
- All 31 chapters of Managing Antidepressant Adverse Events, complete by 30 September
- The finished Managing Antipsychotic Adverse Events series — 21 chapters
- Counselling scripts and copy-paste EMR notes in every chapter
- Every future rapid-decision course at no additional cost
Selected references
- Goodwin GM, Price J, De Bodinat C, Laredo J. Emotional blunting with antidepressant treatments: a survey among depressed patients. J Affect Disord. 2017.
- Peters EM, Balbuena L, Lodhi RJ. Emotional blunting with bupropion and serotonin reuptake inhibitors in three randomized controlled trials for acute major depressive disorder. J Affect Disord. 2022.
- Jawad MY, Fatima M, Hassan U, et al. Can antidepressant use be associated with emotional blunting in a subset of patients with depression? A scoping review of available literature. Hum Psychopharmacol. 2023.
- Lanctôt KL, Ismail Z, Bawa KK, et al. Distinguishing apathy from depression: a review differentiating the behavioral, neuroanatomic, and treatment-related aspects of apathy from depression in neurocognitive disorders. Int J Geriatr Psychiatry. 2023.
- Padala PR, Padala KP, Majagi AS, et al. Selective serotonin reuptake inhibitors-associated apathy syndrome: a cross-sectional study. Medicine (Baltimore). 2020.
- Padala PR, Padala KP, Monga V, Ramirez DA, Sullivan DH. Reversal of SSRI-associated apathy syndrome by discontinuation of therapy. Ann Pharmacother. 2012.
- Corruble E, de Bodinat C, Belaïdi C, Goodwin GM. Efficacy of agomelatine and escitalopram on depression, subjective sleep and emotional experiences in patients with major depressive disorder: a 24-week randomized, controlled, double-blind trial. Int J Neuropsychopharmacol. 2013.
- Fagiolini A, Florea I, Loft H, Christensen MC. Effectiveness of vortioxetine on emotional blunting in patients with major depressive disorder with inadequate response to SSRI/SNRI treatment. J Affect Disord. 2021.
- Christensen MC, Canellas F, Loft H, Montejo ÁL. Effectiveness of vortioxetine for the treatment of emotional blunting in patients with major depressive disorder experiencing inadequate response to SSRI/SNRI monotherapy in Spain: results from the COMPLETE study. Neuropsychiatr Dis Treat. 2024.
- McIntyre RS, Harrison J, Loft H, Jacobson W, Olsen CK. The effects of vortioxetine on cognitive function in patients with major depressive disorder: a meta-analysis of three randomized controlled trials. Int J Neuropsychopharmacol. 2016.
- Dølven S, Moroń M, Eriksen I, Toft JEG, Semkovska M. The comparative efficacy of antidepressant and psychological therapies on cognition in depression: a systematic review and network meta-analysis. Neuropsychol Rev. 2025.
- Armand S, Langley C, Johansen A, et al. Functional brain responses to emotional faces after three to five weeks of intake of escitalopram in healthy individuals: a double-blind, placebo-controlled randomised study. Sci Rep. 2024.
- Christensen MC, Fagiolini A, Florea I, et al. Validation of the Oxford Depression Questionnaire: sensitivity to change, minimal clinically important difference, and response threshold for the assessment of emotional blunting. J Affect Disord. 2021.
- Cuijpers P, Ciharova M, Tong L, et al. Behavioral activation for depression: a comprehensive systematic review and meta-analysis. Clin Psychol Rev. 2026.
- Davies J, Read J. A systematic review into the incidence, severity and duration of antidepressant withdrawal effects: are guidelines evidence-based? Addict Behav. 2019;97:111–121.
The free chapter carries the complete reference list.



Responses