
Your patient’s CYP2D6 type and venlafaxine: who stops it more often?

Slow CYP2D6 metabolizers stopped venlafaxine more often. Should that change your second-line switch?
Two cohorts and 9,067 patients on venlafaxine, read for the prescriber: the answer to our poll, the numbers, and what the guidelines already say.
Harvinder Singh, MD · Board-certified psychiatrist · Psychiatry Education Forum
The 60-second read
Peer reviewed · Observational- Applies toChoosing or troubleshooting venlafaxine, typically after an SSRI hasn't worked, in a patient whose CYP2D6 result you have or could get
- Biggest caveat"Failure" means switching to another antidepressant within a year. The study can't tell whether patients switched because of side effects or because it didn't work
- Second caveatPatients on strong CYP2D6 or CYP2C19 inhibitors (fluoxetine, paroxetine, bupropion and others) were excluded. In your clinic, those drugs can make a normal metabolizer act like a slow one
- Our poll87% predicted slow metabolizers (the answer); 13% predicted fast metabolizers. No one chose "no difference" or "not sure"
1The answer to our poll
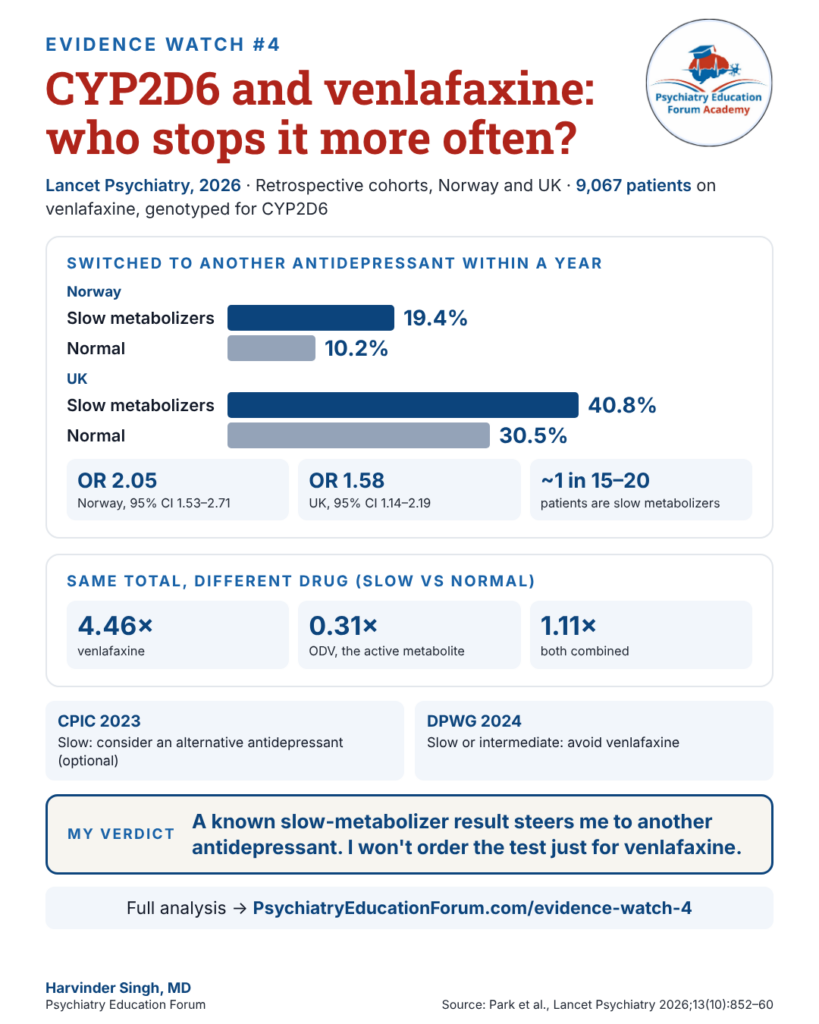
- ASlow metabolizers (CYP2D6 poor)The answer87% votedThe only group with higher switching in both cohorts: 19.4% vs 10.2% in Norway and 40.8% vs 30.5% in the UK, compared with normal metabolizers.
- BFast metabolizers (CYP2D6 ultrarapid)Partly right13% votedA fair answer. Fast metabolizers switched more in Norway (16.8%, OR 1.78), but not in the UK (OR 0.96). The UK fast group was small (80 patients), so this is "not replicated", not "disproved".
- CNeither. Gene type makes no differenceRight premise, wrong conclusion0% votedThe reasoning behind C is real pharmacology: venlafaxine and its main metabolite are both active, so total active drug barely changed in slow metabolizers (1.1 times). But slow metabolizers still switched more. Section 3 looks at one possible explanation, which the study did not test directly.
- DNot sureReasonable0% votedBefore this paper, the evidence linking CYP2D6 to venlafaxine outcomes, rather than drug levels, came from small studies. The authors themselves describe the effect on response as "unclear" before their work.
2The numbers, made usable
Who was studied. Two independent cohorts of adults on venlafaxine, all genotyped for CYP2D6 and CYP2C19:
- Norway: 5,443 patients from a therapeutic drug-monitoring service in Oslo, 2005–2025. Prescribers there received genotype and drug-level reports with dose advice, but no advice to switch drugs.
- UK Biobank: 3,624 patients from routine primary care, where prescribers had no genotype or drug levels. Samples were genotyped later, for research.
Outcome: switching from venlafaxine to another antidepressant within 1 year of the last exposure. Overall, 11.8% switched in Norway and 31.7% in the UK. The two cohorts defined exposure differently, so compare groups within a cohort, not across cohorts.
| CYP2D6 group | Norway: switched | Norway: adjusted OR (95% CI) | UK: switched | UK: adjusted OR (95% CI) |
|---|---|---|---|---|
| Slow (poor) | 72 of 371 (19.4%) | 2.05 (1.53–2.71) Significant | 69 of 169 (40.8%) | 1.58 (1.14–2.19) Significant |
| Intermediate | 237 of 1,899 (12.5%) | 1.25 (1.05–1.50) Significant | 408 of 1,252 (32.6%) | 1.12 (0.96–1.30) Not significant |
| Normal | 310 of 3,048 (10.2%) | Reference | 647 of 2,123 (30.5%) | Reference |
| Fast (ultrarapid) | 21 of 125 (16.8%) | 1.78 (1.06–2.83) Significant | 23 of 80 (28.8%) | 0.96 (0.57–1.57) Not significant |
The two "per 100" figures are my subtraction of the crude rates; the paper reports adjusted odds ratios, not absolute differences. They are a sense of scale, not the effect testing would have.
3Why option C fails: the same total, a different drug
Venlafaxine is "predominantly metabolised by CYP2D6" to O-desmethylvenlafaxine (ODV), an active metabolite, with a secondary contribution from CYP2C19. So in a slow metabolizer, venlafaxine piles up and ODV falls. In the Norwegian drug-level data (240 slow vs 1,855 normal metabolizers):
The authors' explanation, which they did not test directly: venlafaxine and ODV are often treated as equipotent, but they differ in how selectively they block noradrenaline and serotonin reuptake, and venlafaxine gets into the brain more readily. More parent drug may mean more noradrenergic effect and worse tolerability, even when the total looks normal. They also raise cardiotoxicity as a possible concern, citing case reports.
A possible clue, not proof: in Norway, slow metabolizers were kept on lower doses than normal metabolizers (geometric mean 135.7 vs 149.7 mg/day, times-change 0.91, p=0.0005). Norwegian prescribers were sent genotype reports with dose advice, so this could reflect that advice, routine titration or side effects; the study can't separate them. The paper says the doses were "approximately 10% less in both study cohorts", but the UK difference was not significant (0.89 times, p=0.11).
4The detail the abstract leads with, and shouldn't
The abstract highlights that patients who were slow metabolizers for both CYP2D6 and CYP2C19 had 6.11 times higher odds of switching (95% CI 1.81–18.77) in Norway. Read the denominator before quoting it:
- 13 patients, of whom 5 switched. The confidence interval runs from about 2 to about 19.
- In the UK, the same group had 8 patients, too few to estimate anything.
- The striking drug-level figures for this group (venlafaxine about 17 times higher, ODV about 20 times lower) come from 8 patients.
It's a plausible signal that a second slow pathway adds to the first. It is not a number to put in front of a patient.
The authors ran many single-gene and combined comparisons and, by their own statement, applied no adjustment for multiple testing. That doesn't undo the main slow-metabolizer finding, which replicated, but small subgroups and borderline p values should be read as exploratory.
Two smaller points for anyone reading the paper closely. One combined subgroup (CYP2D6 slow × CYP2C19 intermediate) is reported as OR 1.79 (0.98–3.10) with p=0.046. The CI crosses 1 while p is below 0.05, so treat it as uncertain. And the dose analysis includes 5,200 Norwegian patients rather than all 5,443; the paper doesn't account for the other 243.
5What the guidelines already say
This paper did not create the question; the guideline bodies already disagree on it. As summarized and source-checked in our Genetic Testing in Psychiatry course (The patient report and CYP2D6: lower, switch, or ignore):
| CYP2D6 group | CPIC (2023) | DPWG (2024) |
|---|---|---|
| Slow (poor) | "Consider a clinically appropriate alternative antidepressant not predominantly metabolized by CYP2D6." Classification: optional | Avoid venlafaxine; choose an antidepressant not (or less) metabolized by CYP2D6. If it can't be avoided and side effects occur, reduce the dose and monitor |
| Intermediate | No action recommended based on genotype | Avoid venlafaxine (same as slow metabolizers) |
| Fast (ultrarapid) | No action recommended based on genotype | No action required |
- Where this paper sits: it supports both bodies on slow metabolizers. On intermediate metabolizers it is mixed: higher switching in Norway (OR 1.25), not in the UK (OR 1.12, not significant). On fast metabolizers it adds a Norway-only signal that neither body acts on.
- The FDA: its Table of Pharmacogenetic Associations lists venlafaxine for CYP2D6 poor metabolizers ("consider dosage reductions"). The Effexor XR label itself carries no genotype-specific dosing instruction.
- A parallel the authors draw: the same Oslo group earlier linked CYP2C19 genotype to escitalopram failure, also with a U-shaped pattern in which both slow and fast metabolizers switched more.
6What the authors concluded vs what the data support
"CYP2D6 PM status was consistently associated with increased risk of venlafaxine treatment failure in two large, real-life cohorts, suggesting that pre-emptive genotyping could facilitate personalised venlafaxine therapy."
The first half is well supported: the slow-metabolizer signal held in two different health systems, one where prescribers had the genotype and one where they did not. That replication makes it hard to explain by prescribers reacting to a known result.
The second half goes further than the data. "Could facilitate" is a hypothesis. This study did not test genotyping; it looked back. The one randomized trial of CYP2D6-guided venlafaxine dosing we know of (CYSCE, in older adults) did not shorten the time to an adequate drug level. The authors themselves call for prospective studies of genotype-guided dosing or drug choice, and say cost-effectiveness has to be considered.
Disclosure: one of the senior authors (VML) is CEO and a shareholder of HepaPredict, and a co-founder and shareholder of Shanghai Hepo Biotechnology. The other authors declare no competing interests. The study was funded by research councils and foundations, which had no role in the study.
7What it doesn't answer
- Why patients switched: side effects or no response. The study can't separate them.
- Whether testing changes outcomes: one randomized trial, CYSCE, gave prescribers CYP2D6 genotype plus dosing advice for older adults starting nortriptyline or venlafaxine. It found no difference in time to an adequate drug level. No trial has tested whether genotype-guided venlafaxine prescribing prevents switching or improves response.
- Inhibitors in real practice: patients on fluoxetine, paroxetine, bupropion, fluvoxamine or levomepromazine, or on carbamazepine, phenobarbital or phenytoin, were excluded. Cross-tapering from fluoxetine or paroxetine is exactly when many patients start venlafaxine.
- Diagnosis and severity: indication, comorbidity and other medications weren't consistently recorded, so residual confounding is possible.
- Who got into the cohorts: the Norwegian patients came from a drug-monitoring service, which the authors say is probably enriched for patients who were doing poorly. Neither cohort is the same as every patient starting venlafaxine in your clinic.
- Who it applies to: mostly White patients (96.4% in the UK cohort; Norwegian ethnicity not recorded). CYP2D6 allele frequencies differ by ancestry.
Does this change practice?
I won't order CYP2D6 just for venlafaxine. A known slow-metabolizer result now steers me to another antidepressant.
This study doesn't make me test more. The one randomized trial of CYP2D6-guided venlafaxine dosing didn't help, and no trial shows that testing prevents switching. But when a patient already has a result showing a slow metabolizer, two cohorts and both major guidelines now point the same way. I'll pick an antidepressant less dependent on CYP2D6 rather than start venlafaxine and wait to see.
Genetic Testing in Psychiatry
When a report gives a CYP2D6 result, does it change the dose, the drug, or nothing, and who says so? The course works through it chapter by chapter, from whether to order a test to a one-screen drug–gene grid.
Become an Academy member
Full access to every course and Rapid Decision Guide, including Genetic Testing in Psychiatry.
Sources
- Park Y, Lenk HÇ, Zhou Y, Lauschke VM, Molden E. Association between CYP2D6 and CYP2C19 genotypes and venlafaxine treatment failure: a retrospective study on two cohorts from Norway and the UK. Lancet Psychiatry. 2026 Oct;13(10):852–860. doi:10.1016/S2215-0366(26)00238-5. Erratum in: Lancet Psychiatry. 2026 Nov;13(11):e14. doi:10.1016/S2215-0366(26)00305-6. PMID 42716055. Peer reviewed, open access (CC BY 4.0). Retrospective observational study of two cohorts. Figures in this post are from the main paper (Figures 1–2, Tables 1–2) and the supplementary appendix (Tables 2–3).
- Bousman CA, et al. CPIC guideline for CYP2D6, CYP2C19, CYP2B6, SLC6A4 and HTR2A genotypes and serotonin reuptake inhibitor antidepressants. Clin Pharmacol Ther. 2023;114:51–68. doi:10.1002/cpt.2903.
- Beunk L, et al. DPWG guideline for the gene–drug interaction between CYP2D6, CYP2C19 and non-SSRI/non-TCA antidepressants. Eur J Hum Genet. 2024;32:1371–1377. doi:10.1038/s41431-024-01648-1.
- FDA Table of Pharmacogenetic Associations (venlafaxine, CYP2D6), as quoted and source-checked in PEF Academy, Genetic Testing in Psychiatry, Chapters 3 and 5 (October 2026).
- van der Schans J, Hak E, Postma MJ, et al. Effects of pharmacogenetic screening for CYP2D6 among elderly starting therapy with nortriptyline or venlafaxine: a pragmatic randomized controlled trial (CYSCE trial). J Clin Psychopharmacol. 2019;39(6):583–590. doi:10.1097/JCP.0000000000001129. Peer reviewed, randomized controlled trial.
- The escitalopram–CYP2C19 parallel is reported as cited by Park et al. (reference 19: Jukić MM, et al. Am J Psychiatry. 2018;175:463–70), not from the original paper.
Education for clinicians, not medical advice.

Responses